Surgical management of ostomy complications

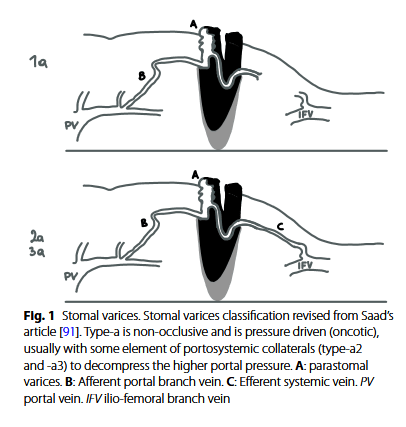
“Most stomal complications are managed non-operatively, through a multidisciplinary and multi-specialist approach. MISSTO in 2021 published the guidelines for the nursing management of stoma-related morbidity. In this context, a key role is played by nurses specialized in stoma care. Sometimes, the conservative approach is not effective to solve the complication, and surgical treatment becomes necessary. The aim of this mapping review is to get a comprehensive overview on the incidence, the risk factors, and the management (conservative and surgical) of the main surgical complications of ostomies,
identifying research gaps and collecting evidence for future research directions.”

Continue reading →

Outcomes of colostomy takedown following Hartmann’s procedure

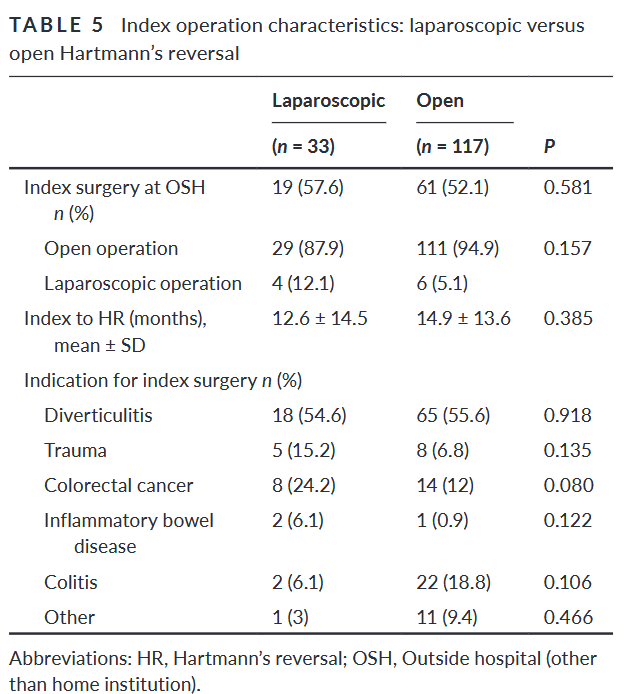
“Reversal of the end colostomy following a Hartmann’s procedure (HP) remains a frequently performed operation, undertaken by colorectal and general surgeons. While Henri Hartmann initially described the procedure in 1921 as a treatment for rectosigmoid cancer, it is now most commonly employed in cases of Hinchey 3 and 4 diverticulitis, where performance of a primary anastomosis is considered unsafe. Trauma, colorectal malignancy, inflammatory bowel disease and ischaemic colitis are other common reasons for performing HP in the USA. Ideally, Hartmann’s reversal (HR) is performed once the patient has recovered from the initial illness in order to re-establish intestinal continuity and avoid a permanent stoma. Historically this procedure has had low rates of success and a high morbidity, leading
to the presence of a permanent stoma in a substantial percentage of patients.

“This paper analyses a large institutional series of reversal of Hartmann’s procedure and provides a new perspective on the outcomes in specialized referral centres. Restoration
of bowel continuity following Hartmann’s procedure is a major surgical undertaking and in previously published literature has been associated with a low probability of success. Although it is associated with significant morbidity we describe a high success rate for restoration of intestinal continuity, at times in patients who have been denied surgery at other locations.”

Continue reading →

The American Society of Colon and Rectal Surgeons Clinical Practice Guidelines for Ostomy Surgery

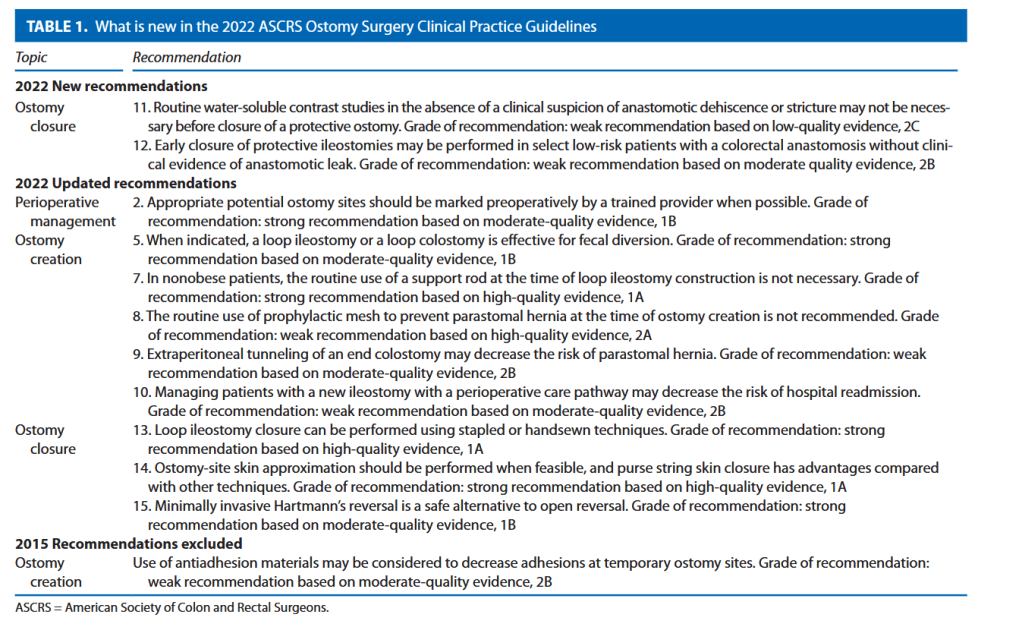
“Statistics regarding ostomy-related metrics remain elusive in the United States because of underreporting and coding limitations. The estimated number of ostomates in the United States is 750,000 to 1 million, with approximately 150,000 new ostomies created each year. Stoma creation has a relatively high rate of associated morbidity, ranging from 20% to 80%; peristomal skin complications and parastomal hernia (PSH) are the most common associ-
ated morbidities. A population-based study using the Michigan Surgical Quality Collaborative, which included 4250 patients, identified a 37% unadjusted surgical complication rate for elective cases involving an ostomy and 55% unadjusted surgical complication rate for emergency cases involving an ostomy. In this study, risk-adjusted stomarelated morbidity rates varied significantly among hospitals, indicating a potential to improve outcomes in outlying institutions.”

Continue reading →

A systematic review of the role of prophylactic ureteric stenting prior to colorectal resections

“There is a need for strategies to reduce the risk of ureteric injury, and to facilitate immediate recognition, during colorectal procedures. The preoperative placement of prophylactic ureteric stents or catheters has long been discussed as a technique that may assist colorectal surgeons in identifying and avoiding the ureters, and in recognising ureteric injury when it occurs.
Debate surrounds this topic, however, with no consensus on the precise benefit of prophylactic ureteric stents, and some concerns regarding potential stent-related complications. Whilst the European Association of Urology (EAU) guidelines state that ‘visual identification of the ureters and meticulous dissection in their vicinity are mandatory
to prevent ureteral trauma during abdominal and pelvic surgery’ (grade A recommendation), the use of ‘preoperative prophylactic stents’ are recommended only ‘in selected cases (based on risk factors and surgeon’s experience)’ (grade B). The American Society of Colon and Rectal Surgeons guidelines in surgery for diverticulitis state ‘ureteral stents are used at the discretion of the surgeon’ (grade 2C).

Table 4 Type of repair and outcomes of ureteric injuries

StudyInjuries (n)Stented and recognised intraoperativelyStented and recognised postoperativelyUnstented and recognised intraoperativelyUnstented and recognised postoperatively
Bothwell [41](open)4/5611/4—primary repair over stent1/4 (stent insertion had failed)—nephrostomy + stent1/4—stent inserted and repair performed1/4 re-exploration and ureteroureterostomy
Beraldo [32](laparoscopic)1/891/89—repair technique not specified–––
Boyan [34] (laparoscopic)None––––
Chahin [35]1/66–1/66 recognised day 2, managed by retrograde stent reinsertion––
Chiu [8]2503/811,071Not evaluated–––
Coakley [3]333/51,125Not evaluated–––
Chong [29]None––––
Hassinger [38]Not evaluated––––
Kutiyanawala [44]5/251No stented patientsNo stented patients3/5—ureteric re-implant × 2 and ureteroureterostomy over stent in × 12/5Nephrostomy + JJ stent × 1 (prolonged recovery, fistula)Relaparotomy + removal of ligasure × 1
Kyzer [33]1/1181/1 repair technique not specified–––
Leff [19]4/1943/4OPEN intraoperative repair1/4—delayed presentation as ureteral-cutaneous fistulaNot evaluatedNot evaluated
Luks [39]2/2612/2 intraoperative repair, type unspecified–––
Merola [28]1/374None1 injury, recognised postoperatively—re-operation (repair not specified)NoneNone
Nam [27]None––––
Pathak [42]None––––
Palaniappa [45] 2012(Open arm)7/46691/7Ureteroneocystostomy1/7Nephrostomy3/7Ureteroneocystostomy × 1, ureteroureterostomy × 22/7Bilateral nephrostomies × 1Ureteroureterostomy × 1
Palaniappa [45]2012(Laparoscopic arm)7/10601/7 Ureteroureterostomy1/7 Ureteroneocystostomy2/7Ureteroneocystostomy × 1Ureteroureterostomy × 13/7Ureteroneocystostomy × 1Nephrostomy × 2
Pokala [30]0––––
Sahoo [40]0    
Senagore [36]0––––
Sheikh [43]Not reported––––
Speicher [31]Not reported––––
Tsujinaka [37]0––––

Continue reading →

Routine evaluation of the distal colon remnant before Hartmann’s reversal is not necessary in asymptomatic patients

“Hartmann’s procedure involves segmental colonic resection with end-colostomy or end-
ileostomy and closure of the distal colonic/rectal remnant (DCRR), which remains in the
pelvis or abdomen as a blind-ending pouch (Hartmann’s pouch). This procedure is
commonly performed in emergency situations in patients who require partial colectomy and
are deemed to be at high risk of complications from a primary bowel anastomosis. The number of patients who undergo takedown of their stoma as a second-stage procedure varies between 56% and 100%.
Preoperative DCRR evaluation by means of contrast and/or endoscopic studies is routinely
requested by many surgeons to exclude leak, stricture, inflammation, and tumors, which
could preclude Hartmann’s reversal. DCRR evaluation is safe and has only minor
disadvantages including cost, radiation exposure, and patient discomfort. However, there is
no clear evidence that this practice affects surgical management or benefits patients. A
previous study reported abnormalities in 16% of routine contrast DCRR studies, although
these altered treatment in only a small minority of cases. In addition, the role of endoscopy
in this setting has not been defined.”

“Between 1993 and 2008, 203 patients underwent reversal of Hartmann’s at a tertiary
referral center. Sixty-eight patients (33%) did not undergo preoperative DCRR evaluation and had comparable demographic characteristics, comorbidities, DCRR length, and perioperative outcomes to 135 patients who underwent preoperative contrast and/or endoscopic studies. After evaluation, 125 (93%) patients had normal findings, seven (5%) patients had abnormal studies that did not impact their management, and three (2%) patients underwent additional procedures.”

Continue reading →

The American Society of Colon and Rectal Surgeons Clinical Practice Guidelines for the Management of Hemorrhoids

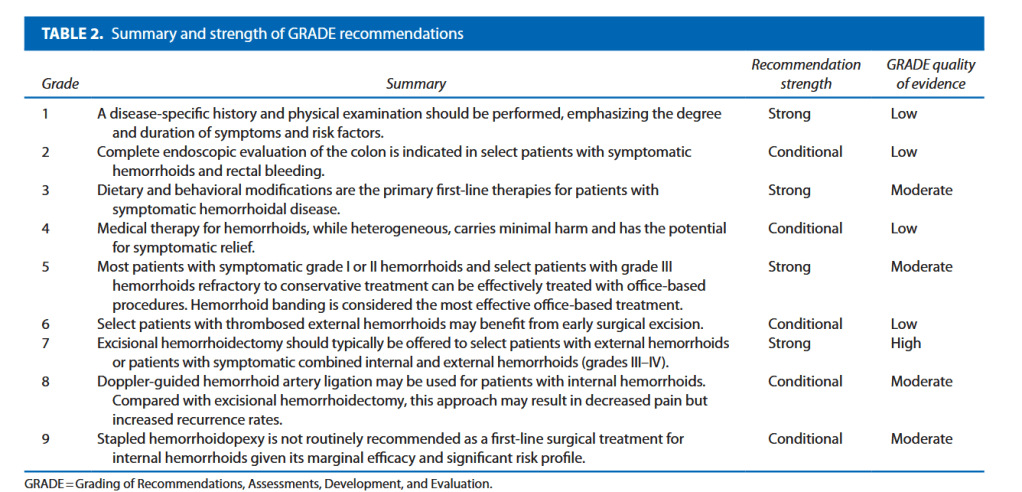
“Hemorrhoids are vascular structures that arise from a channel of arteriovenous connective tissues and drain into the superior and inferior hemorrhoidal veins. Although hemorrhoids are categorized as external or internal based on their relationship with the dentate line, they communicate with one another and often coexist. Symptoms related to hemorrhoids are very common in the Western hemisphere and other industrialized societies. Although published estimates of prevalence vary, hemorrhoidal disease represents one of the most common medical and surgical disease processes encountered in the United States, resulting in more than 2.2 million outpatient evaluations per year. Many diverse symptoms may be, correctly or incorrectly, attributed to hemorrhoids by both patients and referring physicians. As a result, it is important to identify symptomatic hemorrhoids as the underlying source of the
anorectal report and to have a clear understanding of the evaluation and management of this disease process. These guidelines address diagnostic and therapeutic modalities
in the management of hemorrhoidal disease.”

Continue reading →

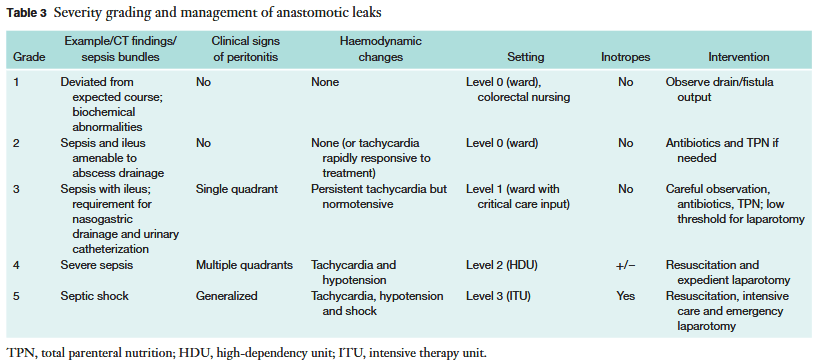
Systematic review of preoperative, intraoperative and postoperative risk factors for colorectal anastomotic leaks

“Anastomotic leak (AL) represents a dreaded complication following colorectal surgery, with a prevalence of 1-19 per cent. There remains a lack of consensus regarding factors that may predispose to AL and the relative risks associated with them. The objective was to perform a systematic review of the literature, focusing on the role of preoperative, intraoperative and postoperative factors in the development of colorectal ALs.”

Continue reading →