We are excited to share a new section titled “Essential Articles for Surgical Residents.”
Keeping up with surgical literature in residency can be challenging. This list was created to serve as an easily accessible, up-to-date, and evidence-based resource for residents.
The content has been curated by faculty from each department and is intended to supplement the standard educational curriculum of each rotation with current and relevant literature.
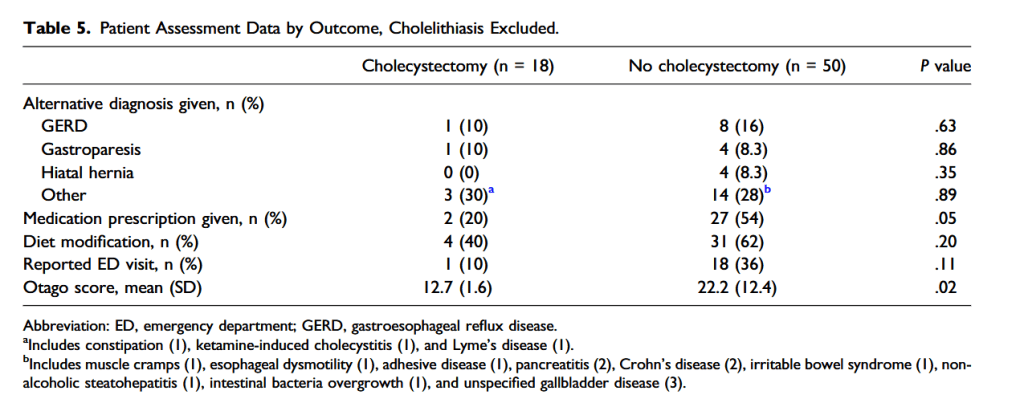
“The intent of this study was to determine if cholecystectomy improved symptoms in patients with a hyperkinetic gallbladder when compared to those who did not undergo surgical intervention and if there were variables predictive of symptom improvement with or without cholecystectomy. The hypothesis was that patients with possible biliary symptoms coupled with a hyperkinetic HIDA evaluation could be alleviated by cholecystectomy.”
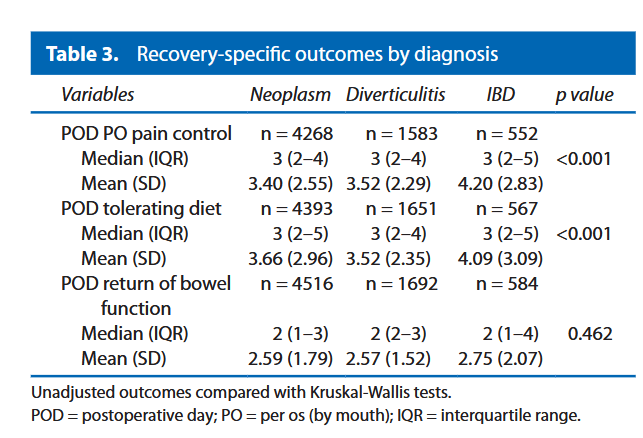
Enhanced recovery protocols (ERPs) refer to perioperative care pathways designed to minimize the physiologic stress of surgery and accelerate post operative recovery. Common pathway elements include comprehensive patient education, multimodal opioid-sparing analgesic techniques, and early postoperative mobilization and feeding. Enhanced recovery protocols permit standardization of perioperative care with evidence-based practices and can promote an interdisciplinary approach. Numerous randomized trials have demonstrated that ERP implementation is associated with decreased hospital length of stay and, in most studies, decreased complications. Recognizing the benefits of ERPs, the American College of Surgeons National Surgical Quality Improvement Program (ACS NSQIP) released novel ERP variables in July 2014. The enhanced recovery in NSQIP variables was optional, and included both process measures related to ERP adherence as well as recovery-specific outcomes.”
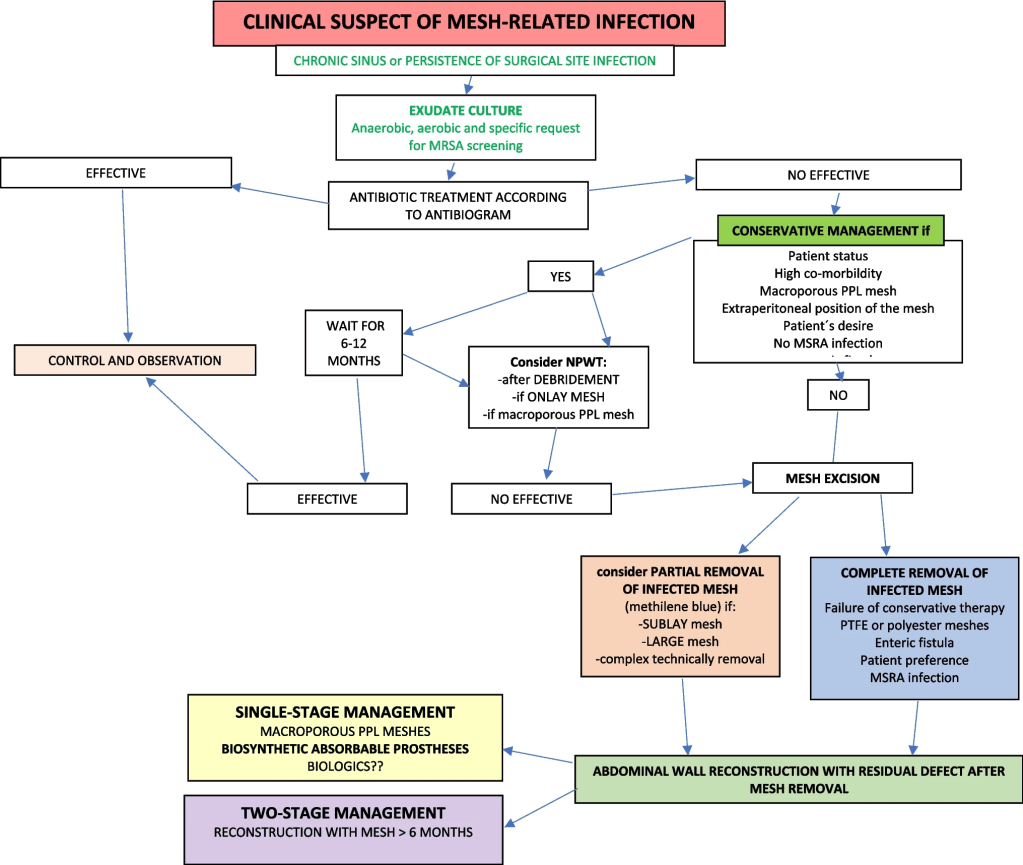
“The management of CMIs involves treatment strategies that range from conservative approaches, such as antibiotics and local wound care, to more aggressive interventions, including partial mesh removal (PMR) or complete mesh removal (CMR). Recent advances advocate for mesh-preserving techniques including meticulous wound irrigation, local antiseptics, and vacuum-assisted closure that may facilitate healing without mesh removal, thus reducing morbidity associated with AWHR.” “The main objective of this article proposes a comprehensive protocol for managing CMIs in AWHR, synthesising our experience about this treatment after 20 years and evidence from recent clinical studies and addressing key management controversies. This algorithm aspires to standardise care practices, reduce treatment failures, and improve patient outcomes in this challenging complication.”
“Post pancreatectomy hemorrhage (PPH) is a rare but fatal complication with reported mortality rates of 16%-50%. It is associated with significant morbidity and mortality, especially when repeat laparotomy is required to control bleeding. Among the causes of PPH, intraabdominal pseudoaneurysm is directly associated with prolonged hospital stay and death due to sudden hemorrhage. An aneurysm is a localized dilatation of the artery and can either be true aneurysm (involves all the 3 arterial layers) or pseudoaneurysm (lack a complete arterial wall or surrounded by soft tissue). An arterial leak is an extravasation or a persistent blood flow following arterial anastomosis or arterial repair into the aneurysm sac. The cause of post-PD pseudoaneurysms is described to be multifactorial. However, it is well known that pancreatic fistula is mostly associated with the development of pseudoaneurysm. Other factors predisposed for its development include iatrogenic trauma of vessel walls during lymphadenectomy, biliary fistula, mechanical irritations by drainage tubes, and intra-abdominal infections that destroy the vessel wall.”
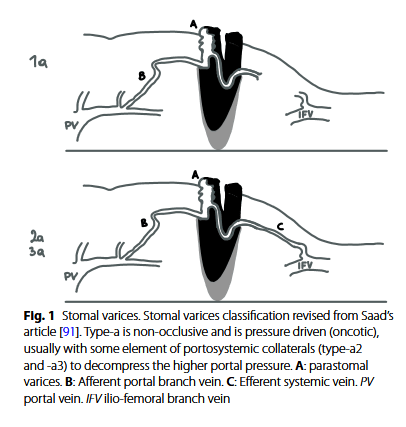
“Most stomal complications are managed non-operatively, through a multidisciplinary and multi-specialist approach. MISSTO in 2021 published the guidelines for the nursing management of stoma-related morbidity. In this context, a key role is played by nurses specialized in stoma care. Sometimes, the conservative approach is not effective to solve the complication, and surgical treatment becomes necessary. The aim of this mapping review is to get a comprehensive overview on the incidence, the risk factors, and the management (conservative and surgical) of the main surgical complications of ostomies, identifying research gaps and collecting evidence for future research directions.”
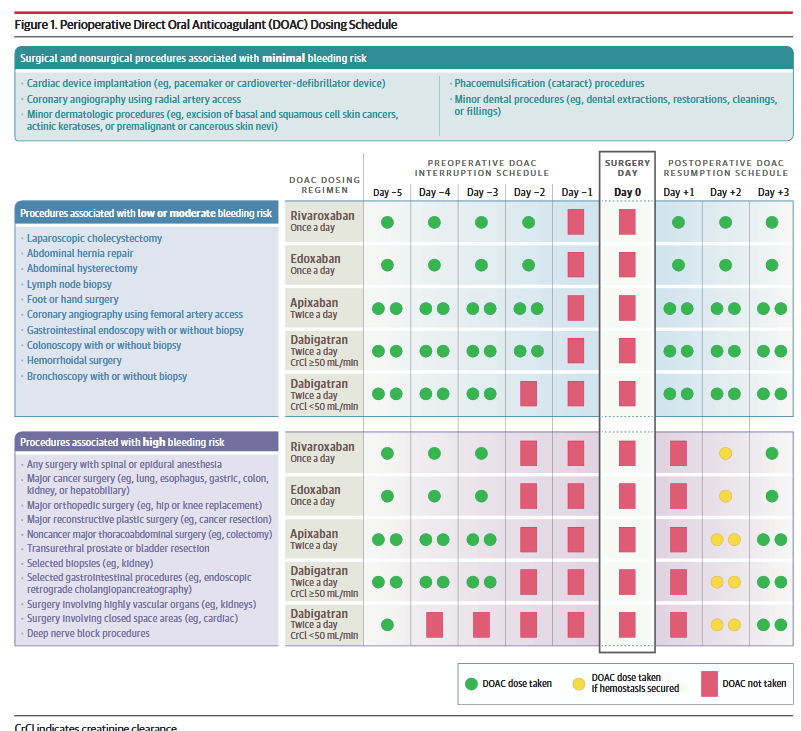
“Direct oral anticoagulants (DOACs), including apixaban, rivaroxaban, edoxaban, and dabigatran, are widely used anticoagulants. Approximately 4 million patients in the US are currently being treated with DOAC therapy. DOACs are indicated for stroke prevention in patients with atrial fibrillation and for the prevention and treatment of venous thromboembolism. For these conditions, DOACs have advantages compared with war- farin that include a lower risk of bleeding, fixed dosing that does not require coagulation test monitoring, and fewer potential drug-drug interactions. Knowing how to advise patients who are taking a DOAC and need a surgical procedure (a surgical operation typically with general/spinal anesthetic) or nonsurgical procedure (a nonsurgical intervention, such as a biopsy or colonoscopy, that typically does not require general/spinal anesthetic) is important because approximately 20% of DOAC-treated patients undergo an elective or urgent procedure annually. Moreover, DOAC use is increasing, especially among older patients for whom a surgical or nonsurgical procedure is most commonly performed.Perioperative DOAC management requires careful decisions about preoperative interruption and postoperative DOAC resumption to minimize the risks of thromboembolism and bleeding. Surgical-site bleeding increases the likelihood of reoperation and delays resumption of anticoagulant therapy, which increases the risk for thromboembolism,”
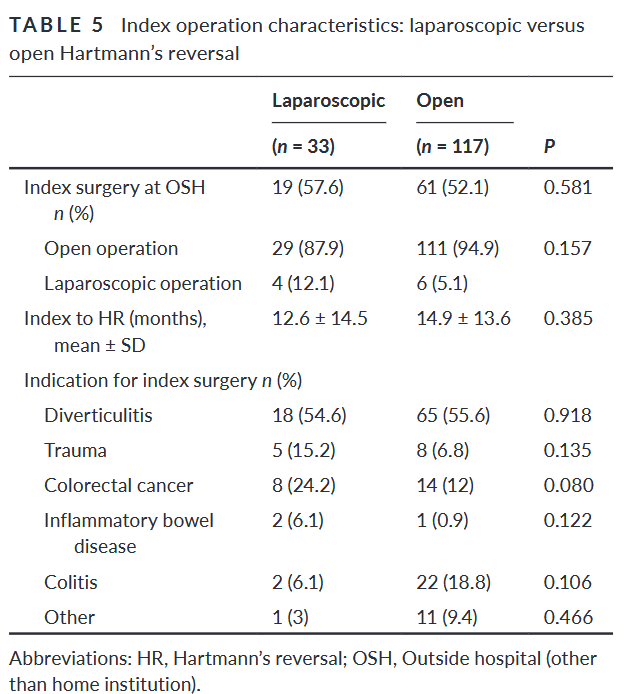
“Reversal of the end colostomy following a Hartmann’s procedure (HP) remains a frequently performed operation, undertaken by colorectal and general surgeons. While Henri Hartmann initially described the procedure in 1921 as a treatment for rectosigmoid cancer, it is now most commonly employed in cases of Hinchey 3 and 4 diverticulitis, where performance of a primary anastomosis is considered unsafe. Trauma, colorectal malignancy, inflammatory bowel disease and ischaemic colitis are other common reasons for performing HP in the USA. Ideally, Hartmann’s reversal (HR) is performed once the patient has recovered from the initial illness in order to re-establish intestinal continuity and avoid a permanent stoma. Historically this procedure has had low rates of success and a high morbidity, leading to the presence of a permanent stoma in a substantial percentage of patients.
“This paper analyses a large institutional series of reversal of Hartmann’s procedure and provides a new perspective on the outcomes in specialized referral centres. Restoration of bowel continuity following Hartmann’s procedure is a major surgical undertaking and in previously published literature has been associated with a low probability of success. Although it is associated with significant morbidity we describe a high success rate for restoration of intestinal continuity, at times in patients who have been denied surgery at other locations.”