One discussion this week involved hepatic resections.
Reference: Strasberg SM, et al. The Brisbane 2000 terminology of liver anatomy and resections. HPB. 2000;2(3):333-339.

One discussion this week involved hepatic resections.
Reference: Strasberg SM, et al. The Brisbane 2000 terminology of liver anatomy and resections. HPB. 2000;2(3):333-339.
One discussion this week involved the Carotid Revascularization Endarterectomy vs. Stenting Trial (CREST).
Reference: Brott TG, et al. Stenting versus endarterectomy for treatment of carotid-artery stenosis. New England Journal of Medicine. 2010 Jul 1;363(1):11-23. doi:10.1056/NEJMoa0912321.
Summary: CREST is an RCT with blinded end-point adjudication whose aim was “to compare the outcomes of carotid-artery stenting with those of carotid endarterectomy among patients with symptomatic or asymptomatic extracranial carotid stenosis” (p.12).
Between December 2000 through July 2008, 2522 patients were enrolled in 108 centers in the US and 9 in Canada. Of those, 1271 patients were randomly assigned to undergo carotid-artery stenting.
Primary findings include (p.18):
One discussion this week included the Asymptomatic Carotid Atherosclerosis Study (ACAS).
Reference: Endarterectomy for asymptomatic carotid artery stenosis. Executive Committee for the Asymptomatic Carotid Atherosclerosis Study. JAMA. 1995 May 10;273(18):1421-1428.
Summary: ACAS was a prospective, randomized trial conducted at 39 sites in the US and Canada between December 1987 and December 1993. Its purpose was to “determine whether the addition of carotid endarterectomy to aggressive medical management can reduce the incidence of cerebral infarction in patients with asymptomatic carotid artery stenosis” (p.1421).
The primary finding was that the risk of ipsilateral stroke and any periopoerative stroke or death over 5 years was 5.1% for surgical patients and 11.0% for medically treated patients (p.1425). Furthermore, those who are good candidates for elective surgery and have carotid artery stenosis of 60% or greater reduction in diameter will have a significantly reduced 5-year risk of ipsilateral stroke “if carotid endarterecomy performed with less than 3% perioperative morbidity and mortality is added to aggressive management of modifiable risk factors” (p.1421).
Additionally, ACAS concluded that CEA reduces the relative stroke risk 66% for men and 17% for women. This difference is perhaps due to higher rates of perioperative complications in women.When arteriographic and perioperative complications are excluded, the risk reduction was 79% for men and 56% for women (p.1427).
One discussion this week involved the North American Symptomatic Carotid Endarterectomy Trial (NASCET).
Reference: Barnett HJM, et al. Benefit of carotid endarterectomy in patients with symptomatic moderate or severe stenosis. New England Journal of Medicine. 1998 Nov 12;339(20):1415-1425.
Summary: NASCET involved 2226 patients with stenosis of less than 70 percent. They were randomly assigned to treatment groups: 1118 to medical therapy, 1108 to surgical therapy (p.1417).
Four patient characteristics are associated with greater benefit from surgery: male sex, recent stroke, recent hemispheric symptoms, and taking 650 mg or more of aspirin per day (p.1419).
NASCET authors explain that the lack of significant benefit for women may be due to their low risk of stroke. Among participants with 50-69% stenosis, the risk of any ipsilateral stroke at 5 years in the medically treated group was 15% for women, and 25% for men. Endarterectomy reduced the risk to 14% for women and 17% for men (p. 1421).
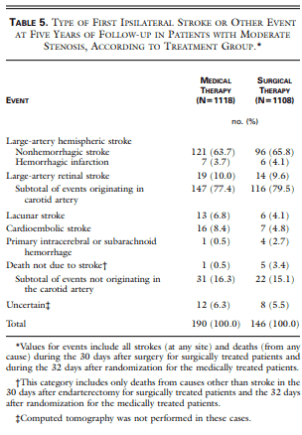
The table below shows the rate of events at 5-year followup:
One discussion this week included parathyroid hormone (PTH) levels.
Reference: Komaba H, et al. Parathyroidectomy and survival among Japanese hemodialysis patients with secondary hyperparathyroidism. Kidney International. 2015 Aug;88(2):350-359. doi: 10.1038/ki.2015.72
Summary: In a nationwide study of 114,064 hemodialysis patients, Komaba et al asked if PTx for severe SHPT improves survival of dialysis patients. They compared patient outcomes by PTH levels, and by those with a history of parathyroidectomy (PTx) (6,6280) and those without PTx (107,436).

(p.353)
Excess PTH is shown to increase cardiac fibrosis; elevations in serum calcium, phophorus, and PTH levels are associated with death and cardiovascular events primarily due to vascular calcification (p.350).

(p.355)
For cardiovascular death, there was a significant increase in the multivariate-adjusted HR for patients with intact PTH levels < 60 pg/ml (HR, 1.11; 95% CI, 1.02–1.20) and those with intact PTH levels >500 pg/ml (HR, 1.41; 95% CI, 1.20–1.64). In contrast, such an increased risk of mortality was not observed in patients with a history of PTx, despite the fact that these patients had severe SHPT preoperatively.
One discussion this week involved the effects of octreotide.
Reference: Octreotide: a drug often used in the critical care setting but not well understood. Chest. 2013 Dec;144(6):1937-1945. doi:10.1378/chest.13-0382.
Summary: While a majority of octreotide is metabolized by the liver, 30-35% of octreotide acetate is excreted in the urine. Thus, octreotide accumulates in patients with moderate to severe renal or hepatic insufficiency.
Compared with SST-14, it exhibits 45-fold more potent inhibition of growth hormone, 11-fold more of glucagon, and 1.3-fold more insulin secretion.

(p.1940)
Octreotide inhibits insulin secretion in the following ways (p.1943):
Additional reading: Adabala M, et al. Severe hyperkalaemia resulting from octreotide use in a haemodioalysis patient. Nephrology, Dialysis, Transplantation. 2010 Oct;25(10):3439-3442. doi:10.1093/ndt/gfq381.
One discussion this week involved the PCI cutoff for CRS/HIPEC for colorectal cancers.
References: Faron M, et al. Linear relationship of Peritoneal Cancer Index and survival in patients with peritoneal metastases from colorectal cancer. Annals of Surgical Oncology. 2016 Jan;23(1):114-119. doi:10.1245/s10434-015-4627-8.
Klaver CEL, et al. Recommendations and consensus on the treatment of peritoneal metastases of colorectal origin: a systematic review of national and international guidelines. Colorectal Disease. 2017 Mar;19(3):224-236. doi:10.1111/codi.13593
Summary: A diagnosis of peritoneal metastases (PM) is generally poor, approximately 5 months if untreated; however, CRS/HIPEC has been shown to increase median survival up to 22 months (Klaver et al, 2017).
Faron et al (2016) explored the relationship between the peritoneal cancer index (PCI) and overall survival in the setting of complete cytoreductive surgery (CCRS) with hyperthermic intraperitoneal chemotherapy (HIPEC). In reviewing the literature, they found that CCRS/HIPEC is indicated for a PCI <12 and not appropriate for a PCI >17. There is an area of indecision in PCIs 12-17.
To bridge this PCI indecision gap, Faron et al (2016) recommend considering the following parameters (p.118):
In a systematic review of 21 guidelines, Klaver et al (2017) found a 71% consensus that CRS/HIPEC is the recommended treatment for PM. There is a need not only for additional evidence, but also an international platform for more trials on CRS/HIPEC and the overall treatment of PM (Klaver et al, 2017).

