Direct Anastomosis of Recurrent Laryngeal Nerves Injured During Thyroidectomy

“Recurrent laryngeal nerve (RLN) paralysis is the most common and significant complication of thyroid or parathyroid cancer surgery. Unilateral RLN paralysis is often due to the adhesions that accompany thyroid cancer. Even with no signs of paralysis preoperatively, a cancerous thyroid gland may be found firmly adherent to RLN intraoperatively, in which case a segment of RLN must be sacrificed for the sake of cancer eradication.””Recurrent laryngeal nerve (RLN) paralysis is the most common and significant complication of thyroid or parathyroid cancer surgery. Unilateral RLN paralysis is often due to the adhesions that accompany thyroid cancer. Even with no signs of paralysis preoperatively, a cancerous thyroid gland may be found firmly adherent to RLN intraoperatively, in which case a segment of RLN must be sacrificed for the sake of cancer eradication.”

Continue reading →

Refractory Variceal Bleed in Cirrhosis

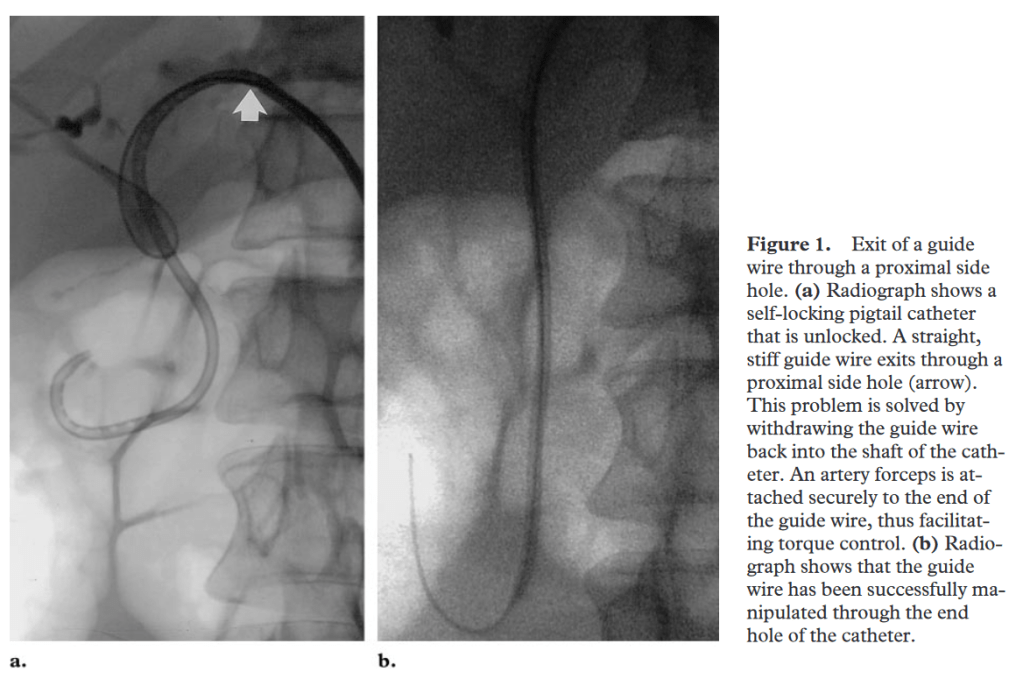
Acute variceal bleeding is the major cause of mortality in patients with cirrhosis. The standard medical and endo-scopic treatment has reduced the mortality of variceal bleeding from 50% to 10–20%. The refractory variceal bleedis either because of failure to control the bleed or failure of secondary prophylaxis. The patients refractory to standardmedical therapy need further interventions. The rescue therapies include balloon tamponade, self-expanding metalstents (SEMS) placement, shunt procedures, including transjugular intrahepatic portosystemic shunt (TIPS),balloon-occluded retrograde transvenous obliteration (BRTO), and endoscopic ultrasound (EUS) guided coiling.

Continue reading →

Indication of a Modified Sugiura Procedurein the Management of Variceal Bleeding

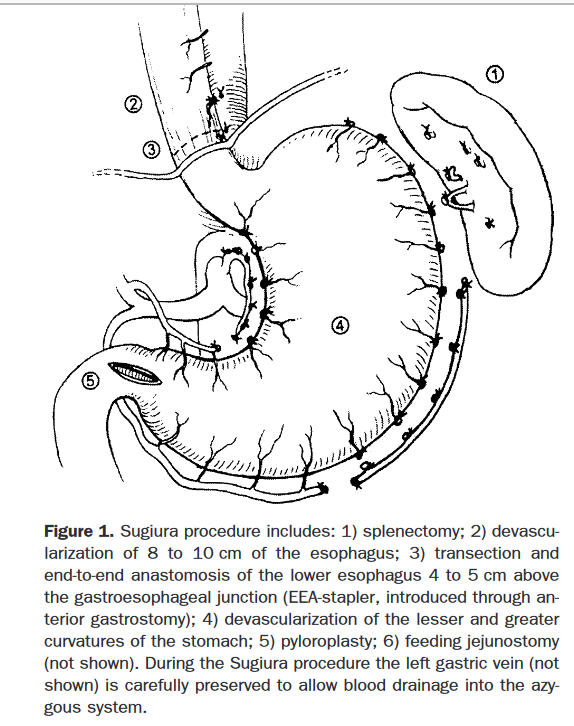
“Study results indicate that the modified Sugiura procedure is an effective rescue therapy in patients who are not candidates for selective shunts, transhepatic porto-systemic shunt, or transplantation. Emergency settings and decreased liver function are associated with an increased morbidity.”

Continue reading →

Mesh placement in ventral hernia repair

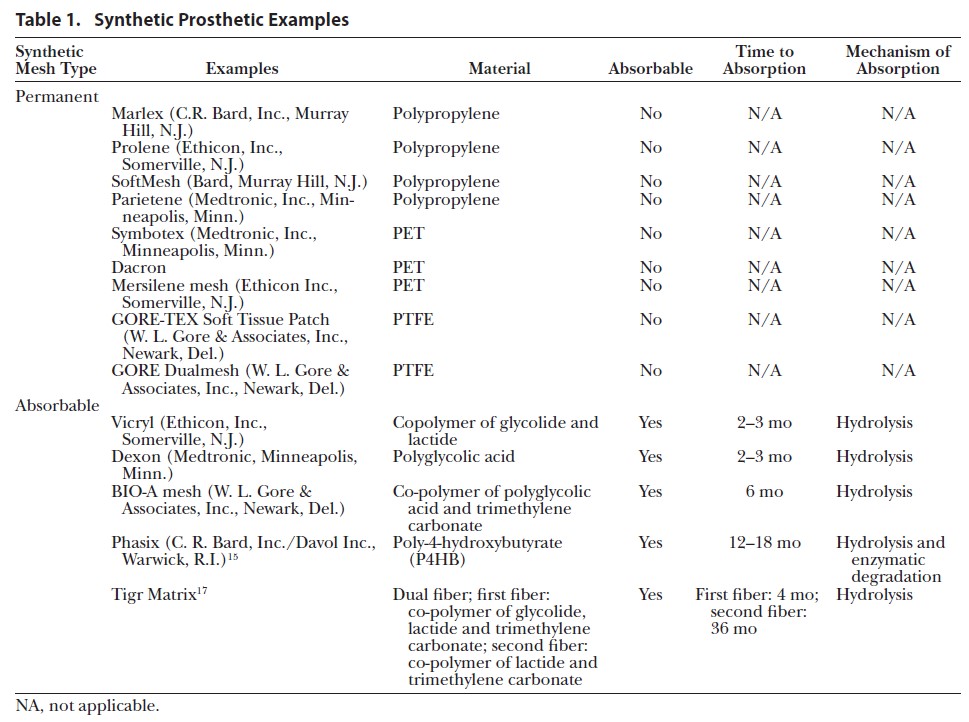
Abdominal wall reconstruction is a relevant and important topic not only in plastic and reconstructive surgery, but in the practice of general surgeons. The ideal anatomic location for mesh placement during the repair of ventral hernias has been debated; however, the most common anatomic locations include onlay, inlay, sublay-retromuscular, sublaypreperitoneal, and sublay-intraperitoneal techniques (Alimi)

(Alimi)
Continue reading →

Anterior versus posterior component separationfor hernia repair in a cadaveric mode

Component separation via both anterior and posterior approaches provide substantial myofascial advancement.In our model, we noted statistically greater anterior fascial medialization after PCS versus ACS as a whole, and especiallyin the upper and mid-abdomen. We advocate PCS as a reliable and possibly superior alternative for linea alba restoration forreconstructive repairs, especially for large defects in the upper and mid-abdomen.

Majumder

Continue reading →