“A plausible explanation for the failure to reduce catheter-related bacteremia with this prophylactic approach probably lies in the mechanism by which catheter-related infection occurs. Thus, it is known that in long-term central venous catheters, bacteria are more likely to be introduced during and following catheter hub manipulation than via spread from the skin insertion site or from tunnel infection. On the other hand, the systemic administration of prophylactic glycopeptides may lead to the emergence of resistant organisms, and Centers for Disease Control and Prevention guidelines recommend against its use [55]. Therefore, the use of systemic glycopeptides to prevent intravascular catheter-related infections is not recommended.” (p. 85)
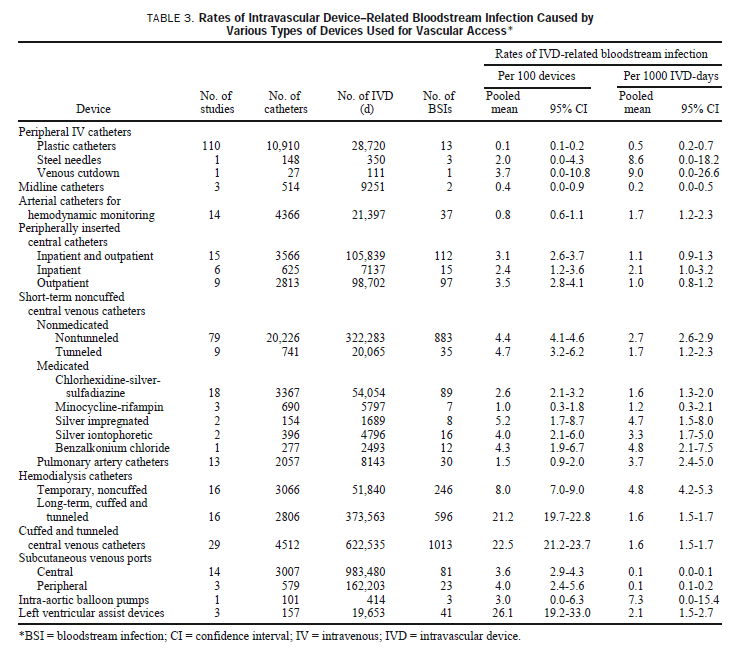
Results: Point incidence rates of IVD-related BSI were lowest with peripheral Intravenous catheters (0.1%, 0.5 per 1000 IVD-days) and midline catheters (0.4%, 0.2 per 1000 catheter-days). Far higher rates were seen with short-term noncuffed and nonmedicated central venous catheters (CVCs) (4.4%, 2.7 per 1000 catheter-days). Arterial catheters used for hemodynamic monitoring (0.8%, 1.7 per 1000 catheter-days) and peripherally inserted central catheters used in hospitalized patients (2.4%, 2.1 per 1000 catheter-days) posed risks approaching those seen with short-term conventional CVCs used in the Intensive care unit. Surgically implanted long-term central venous devices–cuffed and tunneled catheters (22.5%, 1.6 per 1000 IVD-days) and central venous ports (3.6%, 0.1 per 1000 IVD-days)–appear to have high rates of Infection when risk Is expressed as BSIs per 100 IVDs but actually pose much lower risk when rates are expressed per 1000 IVD-days. The use of cuffed and tunneled dual lumen CVCs rather than noncuffed, nontunneled catheters for temporary hemodlalysis and novel preventive technologies, such as CVCs with anti-infective surfaces, was associated with considerably lower rates of catheter-related BSI.
Maki, et al. p. 1162
Conclusions: Expressing risk of IVD-related BSI per 1000 IVD-days rather than BSIs per 100 IVDs allows for more meaningful estimates of risk. These data, based on prospective studies In which every IVD in the study cohort was analyzed for evidence of infection by microbiologically based criteria, show that all types of IVDs pose a risk of IVD-related BSI and can be used for benchmarking rates of infection caused by the various types of IVDs In use at the present time. Since almost all the national effort and progress to date to reduce the risk of IVD-related Infection have focused on short-term noncuffed CVCs used in Intensive care units, Infection control programs must now strive to consistently apply essential control measures and preventive technologies with all types of IVDs.
In conclusion, the available evidence can be summarized as follows:
Prolonged antibiotic prophylaxis in the presence of a wound drain vs. perioperative prophylaxis alone (PICO question 1, comparison 1)
Overall, a low quality of evidence shows that prolonged antibiotic prophylaxis in the presence of a wound drain has neither benefit nor harm in reducing the SSI rate when compared to perioperative prophylaxis alone (single dose before incision and possible intraoperative additional dose/s according to the duration of the operation).
Conclusion: “Our systematic review found that individual physical examination signs (fever, hemorrhagic bullae, and hypotension) were poorly sensitive for diagnosis of NSTI. CT had superior sensitivity and specificity to plain radiography in diagnosing NSTI, but may not be readily available in all centers, and may not be suitable for unstable patients. Finally, the LRINEC score was poorly sensitive for diagnosis of NSTI, suggesting that a low score is not sufficient to rule out the diagnosis.”
Findings: Median follow-up was 3·3 years (range 0·27–5·6). Four patients, all in the preoperative group, did not undergo protocol surgery and were not evaluable for the primary outcome. Of those patients who were eligible and evaluable, wound complications were recorded in 31 (35%) of 88 in the preoperative group and 16 (17%) of 94 in the postoperative group (difference 18% [95% CI 5–30], p=0·01). Tumour size and anatomical site were also significant risk factors in multivariate analysis. Overall survival was slightly better in patients who had preoperative radiotherapy than in those who had postoperative treatment (p=0·0481).