“Acute lower gastrointestinal bleeding (LGIB) is one of the most common reasons for hospitalization in the United States due to a digestive disorder, accounting for over 100,000 admissions annually. Although historically LGIB has referred to a bleeding source originating distal to the ligament of Treitz, small bowel bleeding is considered a separate entity, with a distinct diagnostic and therapeutic algorithm. For the purposes of this clinical practice guideline, LGIB refers to hematochezia or bright red blood per rectum originating from a colorectal source.”
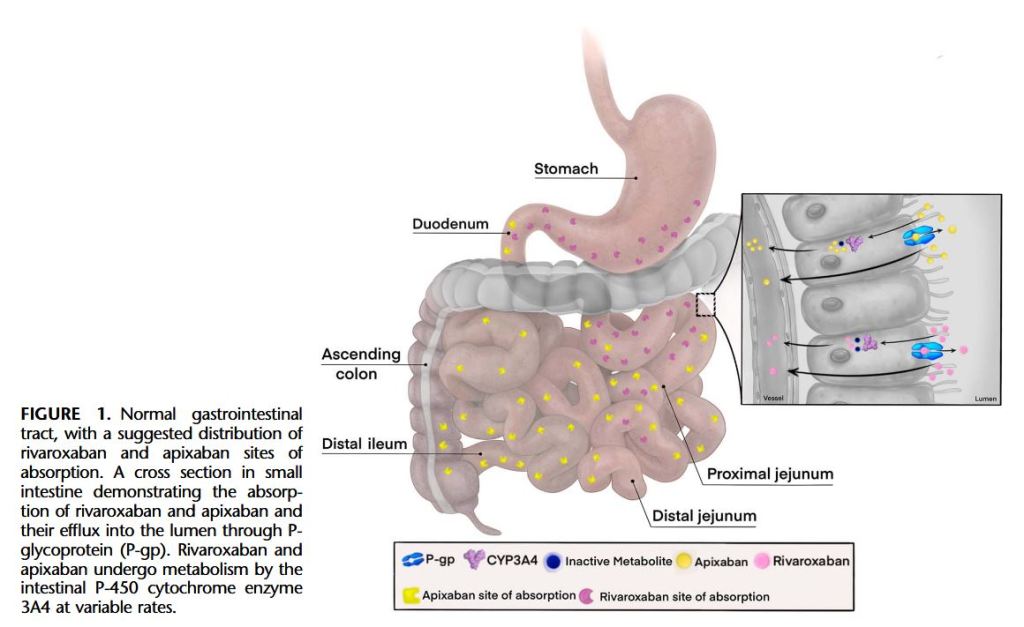
“Direct-acting oral anticoagulants (DOACs) are recommended over vitamin K antagonists (VKAs) for both the treatment of venous thromboembolism (VTE) and the prevention of stroke and systemic embolism in nonvalvular atrial fibrillation (AF). Two classes of DOACs are currently approved by the European Medication Agency and the US Food and Drug Administration: the direct factor Xa inhibitors, including rivaroxaban, apixaban, and edoxaban, and a direct thrombin inhibitor, dabigatran. 5 Unlike the VKAs, which have a narrow therapeutic range and require dose individualization to maintain a therapeutic international normalized ratio, DOACs have a wide therapeutic range, allowing for fixed dose regimens. Efficacious DOAC doses were determined in Phase III trials that were designed based on studies conducted in healthy subjects with an intact gastrointestinal tract (GIT). Therefore, it is difficult to extrapolate outcomes with DOAC treatment to patients who undergo surgical resection or bypass of the GIT, which may result in alteration of absorptive capacity. Because of the potential of reduced efficacy, the Update on Guidelines for the Management of Cancer-Associated Thrombosis has recently expressed concerns regarding the use of DOAC in patients with proximal GIT resection.”
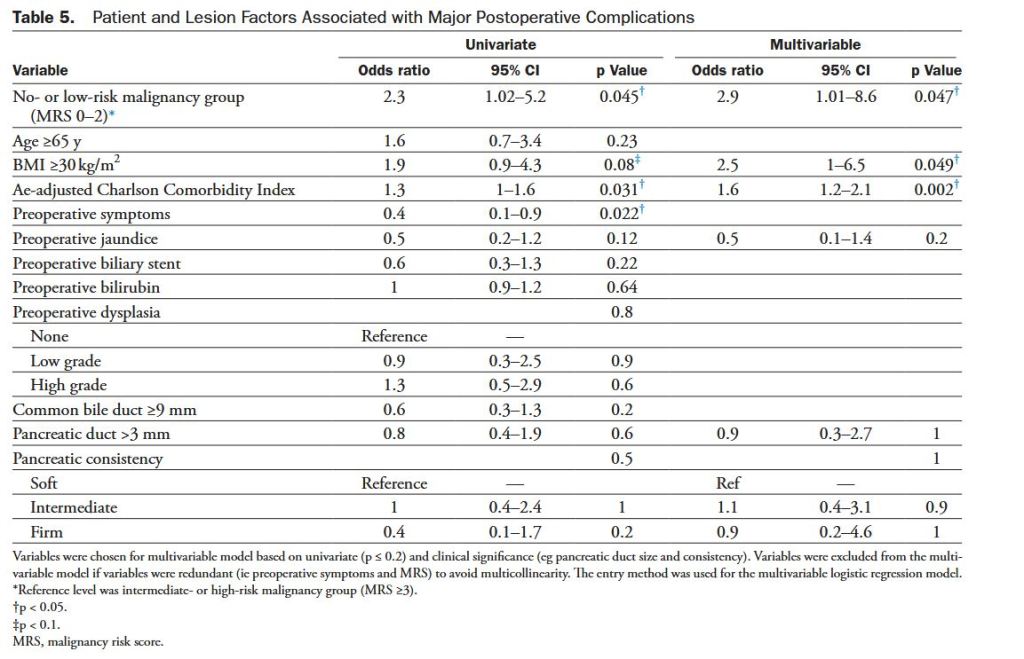
“Periampullary adenomas (PA), including both ampullary adenomas (AAs) and duodenal adenomas (DAs), are benign or premalignant mucosal lesions that are either hereditary, most associated with familial adenomatous polyposis (FAP) syndrome, or sporadic, with no known genetic predisposition. In both cases, these uncommon mucosal-based lesions carry malignancy risk and present management dilemmas when not amenable to endoscopic removal requiring surgical resection. FAP-related PAs are typically large and multifocal and often managed using the Spigelman classification, a point-based system that alerts the clinician of malignancy risk. This classification guides the decision toward continued endoscopic surveillance vs resection vis-à-vis pancreaticoduodenectomy (PD, also known as the “Whipple procedure”). No such scoring system exists for non-FAP-related PAs.”
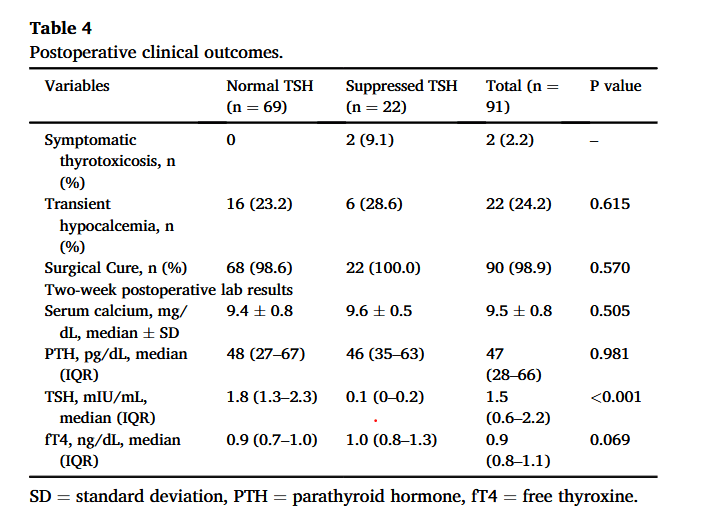
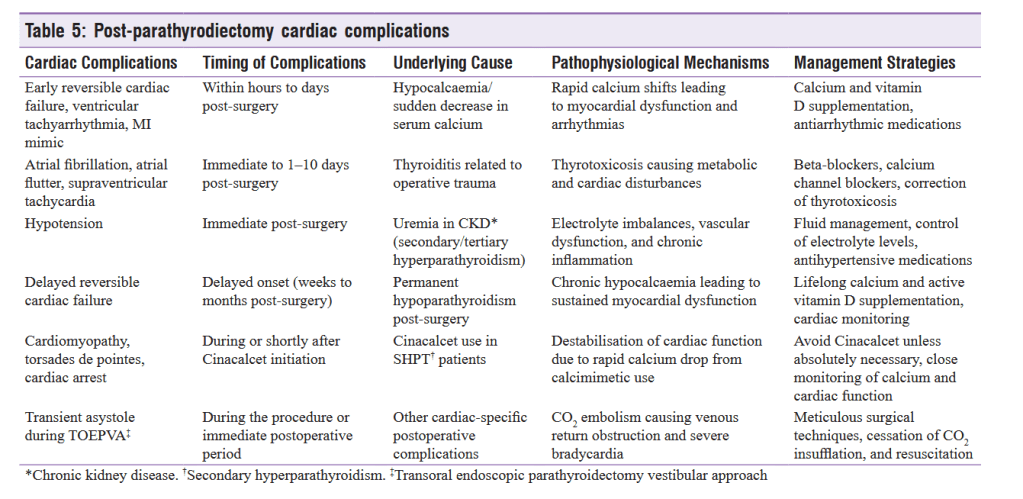
“Thyrotoxicosis has been reported as a postoperative complication of parathyroidectomy (PTx), attributed to palpation thyroiditis. Palpation thyroiditis was first described by Carney et al., in 1975 as a pathologic response to the traumatic injury of thyroid follicles, characterized by multifocal granulomatous folliculitis. The existing cohort studies in post-PTx thyrotoxicosis are limited. A prospective study of patients who underwent PTx for primary and secondary HPT reported that the incidence rate of thyrotoxicosis after PTx was 31.2 % and 77 %, respectively. The clinical significance of post-PTx thyrotoxicosis remains controversial. While various manifestations of thyrotoxicosis, including tremors, palpitations, new-onset atrial fibrillation, and angina pectoris mimicking myocardial infarction, were described by case reports, Stang et al. in a cohort study reported that only 15 % of patients developed symptoms of thyrotoxicosis 1–2 weeks after the operation. They further concluded that the degree of neck dissection appeared explanatory but did not specify which maneuvers were contributory.”
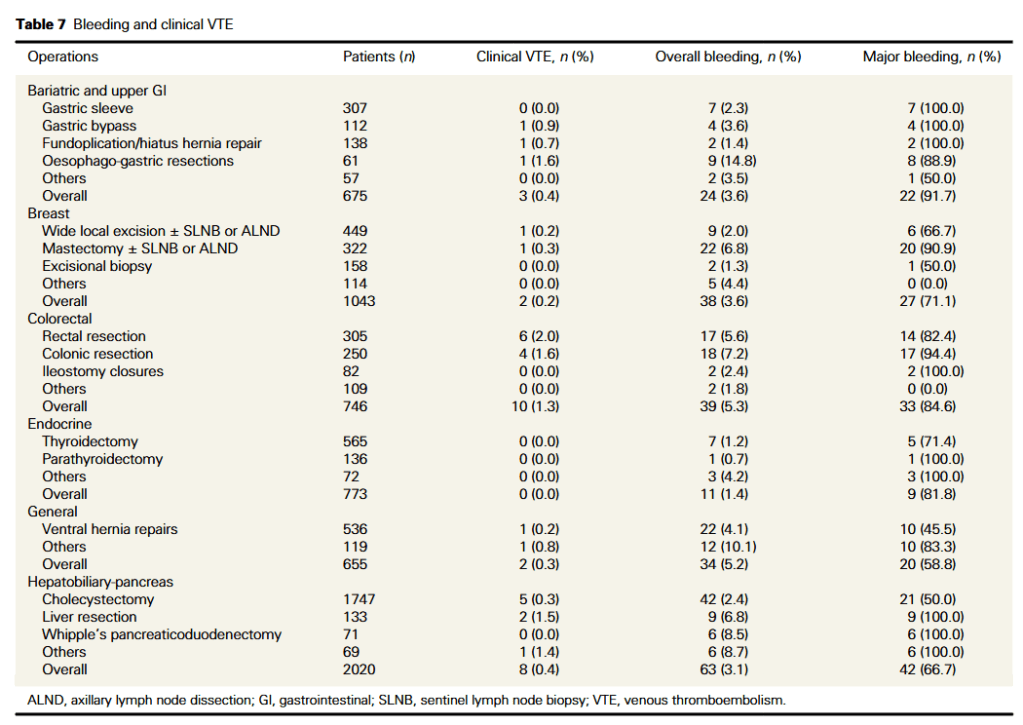
“General surgical patients who undergo major operations are at risk of venous thromboembolism (VTE). This incurs significant morbidity and healthcare costs. Therefore, the Royal Australasian College of Surgeons and other regulatory bodies recommend routine thromboprophylaxis. Moreover, considerations for thromboprophylaxis is an integral part of theatre timeout performed prior to any operation.”
“In this study, we extend the observations made from our multicentre survey by quantifying the heterogeneity of perioperative thromboprophylaxis across all major general surgical operations, and placing them in context of their bleeding and VTE risk. Findings from this study will highlight areas of practice with the greatest variability, allow surgeons to benchmark their practices against that of their colleagues and focus future research to optimize perioperative thromboprophylaxis.”
“Parathyroidectomy (PTX) is primarily performed to treat primary and secondary hyperparathyroidism (HPT) and has been shown to reduce cardiac risk factors, including ECG abnormalities, 2D-echo abnormalities, arrhythmias, and NT-proBNP levels Cardiac complications, though rare, can occur in patients undergoing thyroidectomy. In a US-based cohort of 3,575 patients, approximately 0.2%–0.3% developed congestive heart failure (CHF) during follow-up. A study by Kravietz et al. found that while readmission rates were lower in primary HPT (PHPT) patients (5.6%) compared to secondary HPT (SHPT) patients (19.4%), heart failure was more prevalent in PHPT patients (10.8%) compared to SHPT patients (3.9%). Additionally, patients with existing CHF undergoing PTX have a higher likelihood of readmission. Although cardiac complications are rare, they can occasionally be fatal.”
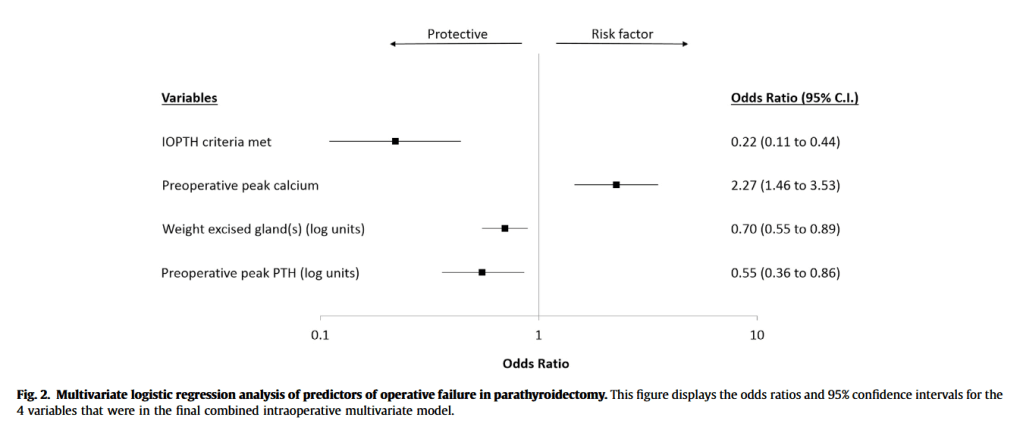
“Little is known about patient-level predictors of operative failure and persistent primary hyperparathyroidism (PHPT). Previous studies have attributed operative failure to inadequate preoperative imaging localization. Achievement of IOPTH criteria is a known predictor of operative success, though the final target IOPTH level is not agreed upon. Some researchers contend that final IOPTH levels should fall into the normal range, while others recommend lower levels. The independent contributions of preoperative localization, IOPTH biochemical cure, and preoperative biochemical severity to operative success are unclear. Better understanding of the relationship.”


 Surgical Focus
