Bacterial translocation as a cause of surgical sepsis

‘The term ‘bacterial translocation’ is used to describe the passage of viable resident bacteria from the gastrointestinal tract to normally sterile tissues such as the mesenteric lymph nodes and other internal organs.7 The term also applies to the passage of inert particles and other macromolecules, such as lipopolysaccharide endotoxin, across the intestinal mucosal barrier.’

‘Bacterial translocation has been shown to occur in various patient populations.6 As already stated, it occurs in patients undergoing elective abdominal surgery, organ donors and those with intestinal obstruction, colorectal cancer, ischaemia–reperfusion injury shock and pancreatitis. Many authors suggest an increased prevalence in patients with obstructive jaundice, those receiving parenteral nutrition and the malnourished, but the evidence for this is limited. Interestingly, translocation, assessed by endotoxin or bacterial culture of portal or systemic blood, has only rarely been demonstrated after trauma’

Continue reading →

Role of bacterial translocation in post op infection after GI surgery.

‘The incidence of postoperative sepsis has increased in the past decades, with the proportion of severe sepsis cases rising to unprecedented levels. Cases of sepsis are noted both after elective and emergency surgeries, but in the cases of elective surgeries, mortality is not respectively affected. Gastrointestinal perforation is the most common surgical condition requiring immediate surgical intervention. More specifically, colonic perforation may cause peritonitis through the spread of bacteria from the intestines, and, therefore, there is a high risk for further bacterial spread via blood flow.”

Figure 1 Mechanism of bacterial translocation after major gastrointestinal surgery.
Continue reading →

Bacterial Translocation in Abdominal Trauma and Postoperative Infections

There is higher risk of BT in trauma patients, and it is associated with a significant increase of postoperative infections. An abdominal trauma index ≥10 was found to be associated with the development of BT. This is the first study describing BT among patients with abdominal trauma, where causality is confirmed at molecular level.

Continue reading →

Bacterial translocation

‘Bacterial translocation (BT) describes the passage of bacteria from the gastrointestinal tract to normally sterile tissues such as the mesenteric lymph nodes (MLNs) and other internal organs. The clinical and pathophysiological significance of BT remains controversial. This report describes results obtained over a 13-year period of study.”

Table 1. Patients characteristics and indication for laparotomy

Type of surgery
 Emergency185
 Elective742
Diagnosis
 Malignancy543 (58·6)
  Upper gastrointestinal26
  Pancreaticohepatobiliary16
  Colorectal402
  Other99
 Inflammatory bowel disease94 (10·1)
  Crohn’s disease44
  Ulcerative colitis50
 Benign upper gastrointestinal54 (5·8)
 Benign pancreaticohepatobiliary44 (4·7)
 Benign lower gastrointestinal105 (11·3)
 Abdominal aortic aneurysm87 (9·4)
Continue reading →

Dexamethasone treatment for the acute respiratory distress syndrome

“Acute respiratory distress syndrome (ARDS) is an intense inflammatory process of the lungs in response to acute pulmonary and systemic insults. There are no proven effective, specific pharmacological therapies for ARDS based on the results of randomised clinical trials. Despite no conclusive results, it remains clinically and biologically plausible that corticosteroids might benefit patients with ARDS in the early phase of their disease process, a situation that has not been evaluated in most randomised controlled trials. Paradoxically,
these hormones are given to patients with septic shock and pneumonia, both causes of ARDS.”

Continue reading →

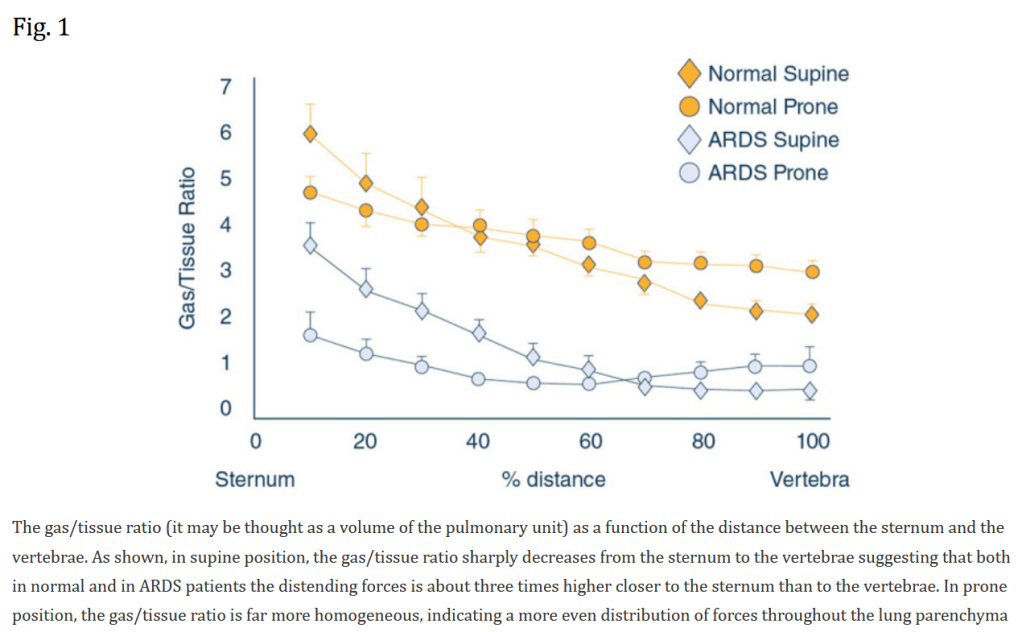
Prone position in ARDS patients

“In ARDS patients, the change from supine to prone position generates a more even distribution of the gas–tissue ratios along the dependent–nondependent axis and a more homogeneous distribution of lung stress and strain. The change to prone position is generally accompanied by a marked improvement in arterial blood gases, which is mainly due to a better overall ventilation/perfusion matching. Improvement in oxygenation and reduction in mortality are the main reasons to implement prone position in patients with ARDS.”

Continue reading →

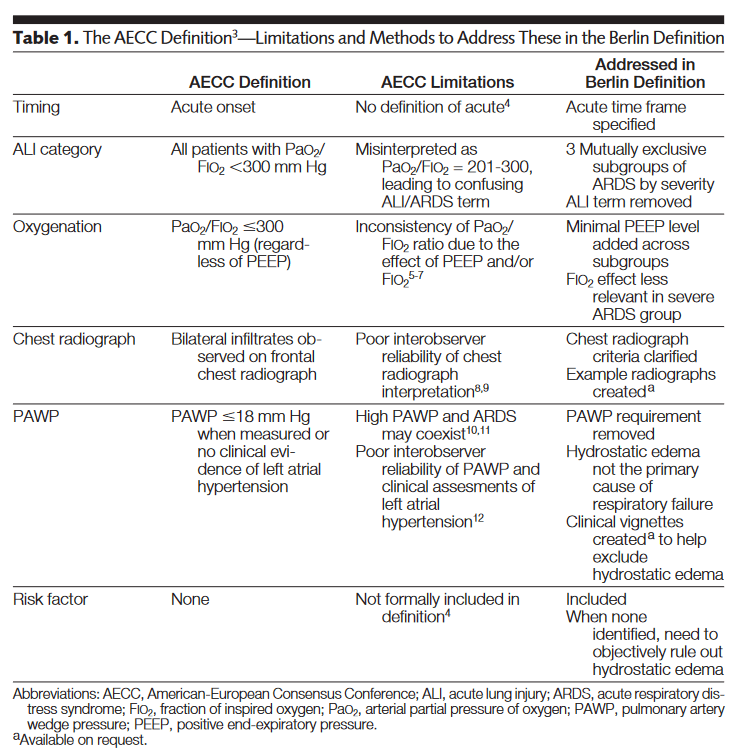
Acute Respiratory Distress Syndrome: The Berlin Definition

“The acute respiratory distress syndrome (ARDS) was defined in 1994 by the
American-European Consensus Conference (AECC). In 2011 (an initiative of the European Society of Intensive Care Medicine endorsed by the American Thoracic Society and the Society of Critical Care Medicine) developed the Berlin Defnition, focusing on feasibility, reliability, validity, and objective evaluation of its performance. Using the Berlin Definition, stages of mild, moderate, and severe ARDS were associated with increased mortality (27%; 95% CI, 24%-30%; 32%; 95% CI, 29%-34%; and 45%; 95% CI, 42%-48%, respectively; P.001) and increased median duration of mechanical ventilation in survivors (5 days; interquartile [IQR], 2-11; 7 days; IQR, 4-14; and 9 days; IQR, 5-17, respectively; P.001).”

Continue reading →