Symptomatic perioperative venous thromboembolism is a frequent complication inpatients with a history of deep vein thrombosis

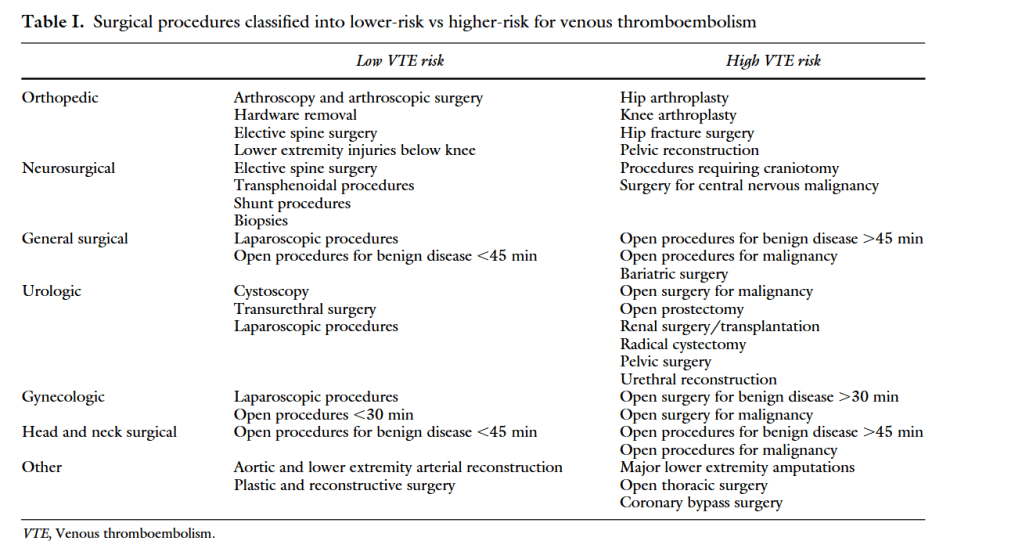
“Perioperative venous thromboembolism (VTE) is a frequent complication in patients who undergo major surgical procedures. The risk for thromboembolism is increased in patients with advancing age, malignancy, inherited and acquired thrombophilic conditions, and in those patients who undergo certain higher-risk surgical procedures (for example: total hip arthroplasty, total knee arthroplasty, and abdominal cancer operations). A history of deep vein thrombosis (DVT) or pulmonary embolism (PE) frequently is cited as a risk factor for subsequent recurrence around the time of surgery. However, the incidence of perioperative VTE recurrence in patients with a history of lower extremity deep vein thrombosis is not well studied.”
Continue reading

Operative Outcomes for Polycystic Liver Disease

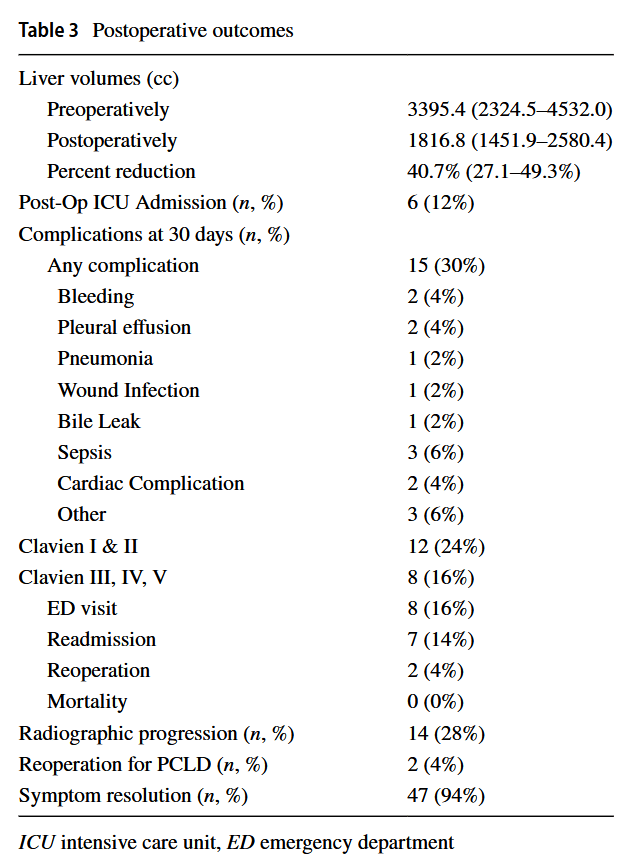
“Currently, there are no effective medical therapies proven to benefit symptomatic PCLD. Some data exist to support the use of somatostatin analogs in the treatment of hepatomegaly due to PCLD; however, the durability of their efficacy remain in question. Vasopressin receptor antagonists, ursodeoxycholic acid, and protein kinase inhibitors
have also been investigated in the management of symptomatic PCLD, but none has been shown to reduce liver volume sufficiently for symptom improvement. With the lack of medical therapies, management of advanced PCLD relies on procedural intervention. Cyst aspiration may be sufficient in patients with a single large cyst; however, with the innumerable cysts present in PCLD, aspiration is frequently ineffective.”

Continue reading

Laparoscopic vs. open feeding jejunostomy

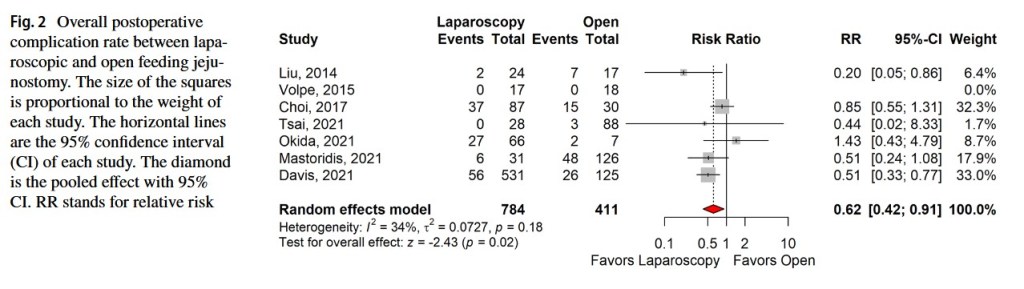
“Feeding jejunostomy is conventionally done via laparotomy. However, since laparoscopic jejunostomy was introduced in 1990, the procedure is constantly advancing with new techniques and devices. It was demonstrated to be a safe, feasible, and cost-effective technique with comparable complication rate to open feeding jejunostomy.”

“In addition, compared with the conventional open procedure, the laparoscopic approach has the inherit merits of smaller incisions, better cosmesis, less postoperative pain, and earlier recovery. With the aim of achieving early enteral feeding and a reduction in postoperative morbidity, any complications arising from the procedure will jeopardize its benefits, incur additional costs, and delay subsequent oncologic treatment.”

Continue reading

Safety of mechanical chest compression devices AutoPulse and LUCAS in cardiac arrest

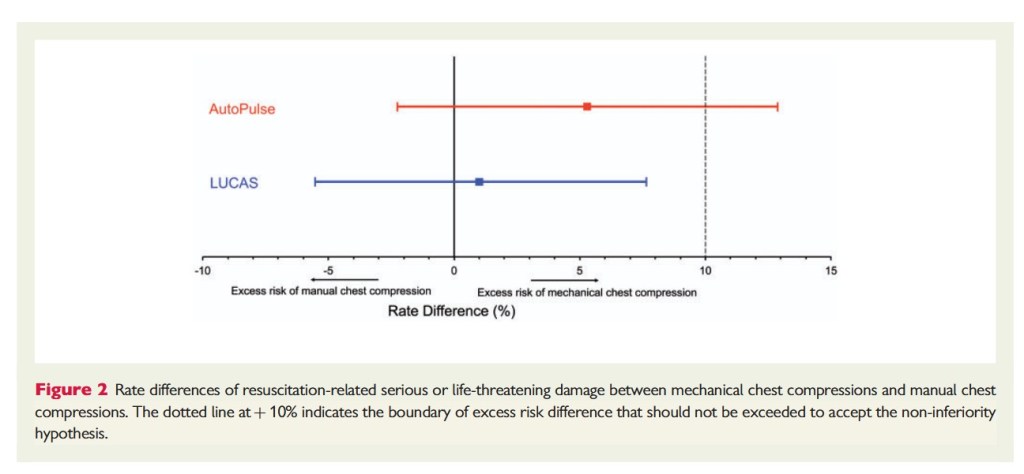
“Mechanical chest compression devices are designed to perform chest compressions at specified rate and depth and therefore were expected to improve outcome. There are at
present two widely used and Food and Drug Administration-approved devices: the AutoPulse, a load-distributed band device that rhythmically compresses and restricts the chest wall and the LUCAS, a piston device with a cup that is placed in the centre of the chest and pushes the sternum down over a distance of 5.2 cm and pulls back to the neutral position. Significant improvement of aortic blood pressure and coronary perfusion pressure is documented in humans from the AutoPulse compared with manual chest compressions. Chest compression with LUCAS resulted in significantly higher end-tidal carbon dioxide in humans compared with manual chest compressions. For several years, only one randomized clinical trial with the AutoPulse was available (ASPIRE), which was terminated after interim analysis because of a trend to reduced survival to discharge compared with manual control CPR. None of the more recent randomized clinical trials demonstrated survival benefit of AutoPulse or LUCAS over manual controls. Anecdotal and possibly biased observations in our hospital and a published letter suggested increased
damage caused by mechanical chest compression devices.”

Continue reading

Medical Management and Revascularization for Asymptomatic Carotid Stenosis

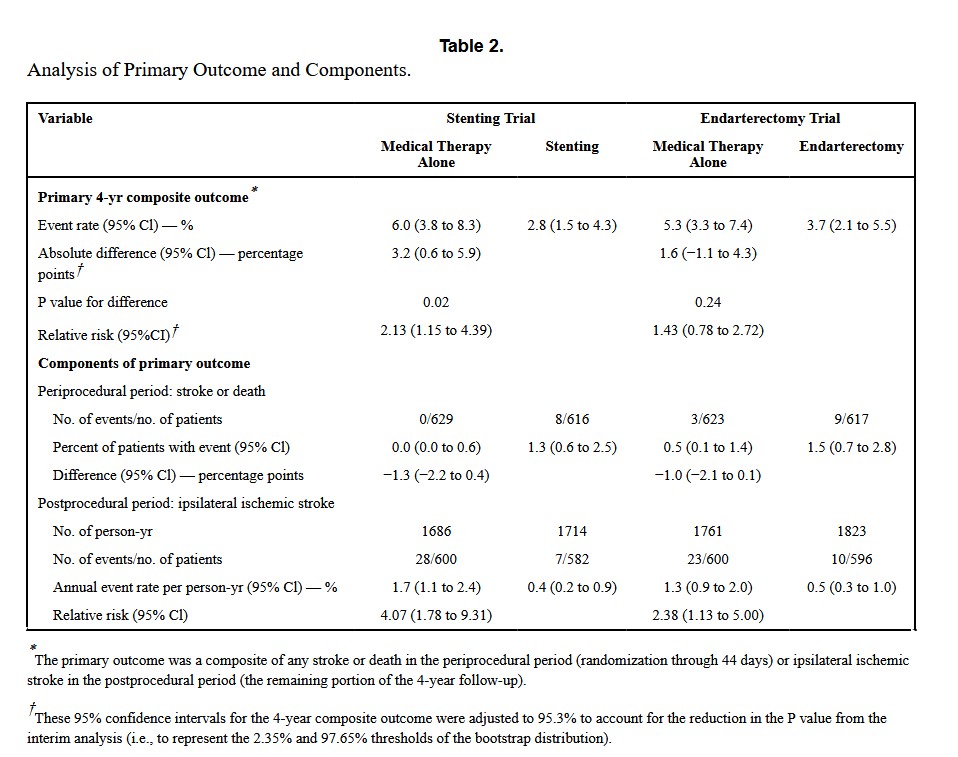
“The treatment of high-grade carotid-artery stenosis varies considerably internationally. Some countries limit revascularization primarily to patients with symptoms, whereas others more commonly recommend that asymptomatic patients undergo revascularization. In the United States, 75 to 80% of patients who undergo carotid-artery stenting or endarterectomy are asymptomatic. Randomized trials from the 1990s and early 2000s showed that carotid
endarterectomy led to a lower risk of stroke among asymptomatic patients with high-grade
stenosis than medical therapy. Improvements in carotid endarterectomy, carotid-artery
stenting, and medical therapy and the results of two recent small trials have challenged
our understanding of appropriate treatments. Here, we present results from the Carotid
Revascularization and Medical Management for Asymptomatic Carotid Stenosis Trials
(CREST-2), which tested whether carotid artery stenting or carotid endarterectomy plus
intensive medical management would be superior to intensive medical management alone
for preventing stroke in patients with high-grade carotid stenosis without recent stroke
symptoms.”

Continue reading

Tranexamic Acid Use in Breast Surgery

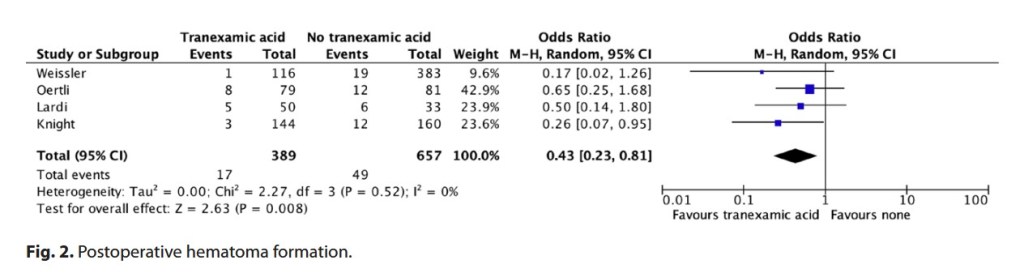
“Tranexamic acid (TXA) is an antifibrinolytic agent that competitively inhibits the conversion
of plasminogen to plasmin. TXA is also believed to have an anti-inflammatory effect and may improve platelet function under certain circumstances. TXA has increasingly gained recognition in perioperative use to mitigate the risk of postoperative bleeding. Originating in the field of anesthesiology, TXA is used to control surgical, traumatic, and postpartum hemorrhage. Meanwhile, perioperative TXA administration has been established in orthopedic and cardiothoracic surgery. It is also becoming popular in plastic surgery, especially regarding craniomaxillofacial procedures. Although the evidence on
the use of TXA in breast surgery is improving, its value still needs further investigation.”

Continue reading

Aspiration versus peritoneal lavage in appendicitis

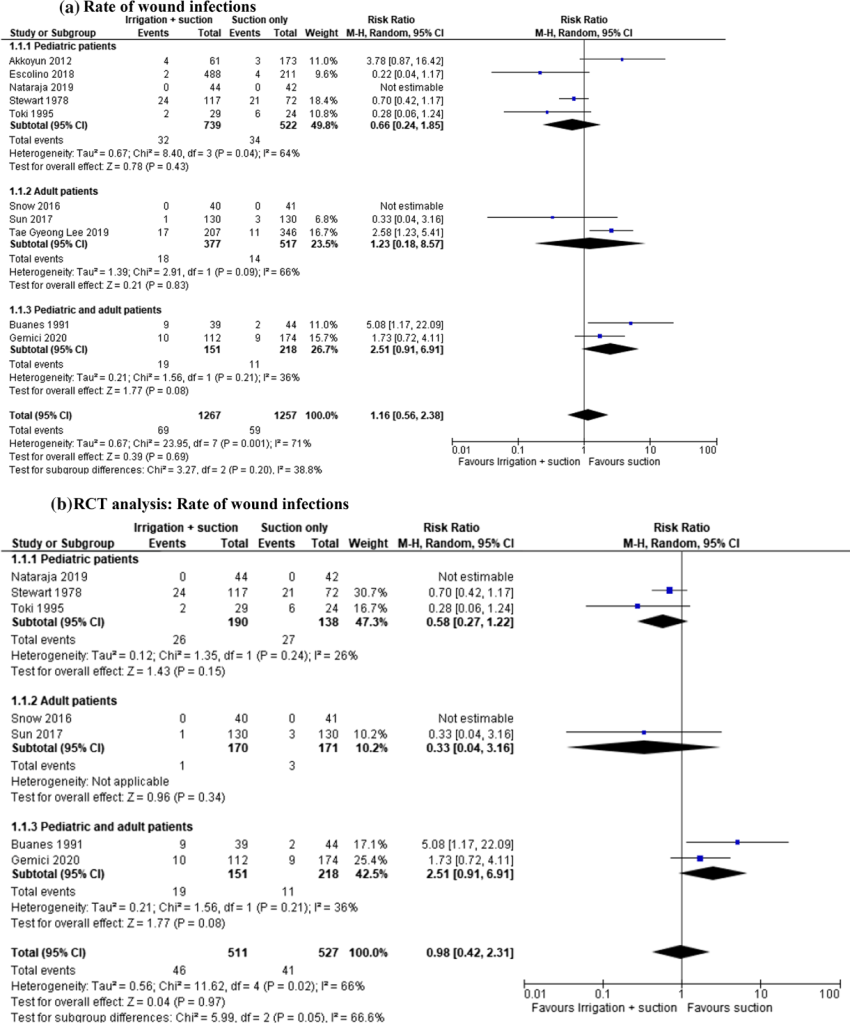
“The management of IAA remains controversial with different strategies suggested to decrease its incidence: antibiotic prophylaxis, post-operative antibiotic therapy, peritoneal irrigation with saline solution or suction only of the abscess/purulent liquid without irrigation of the cavity during appendectomy. In the literature, many studies address this topic; however, currently there is no evidence to clearly demonstrate the effectiveness of peritoneal irrigation over suction only. Italian guidelines recommend thorough peritoneal lavage (6–8 L of warm saline) and aspiration to minimize the IAA rate in complicated appendicitis. The recent WSES (World Society of Emergency Surgery) guidelines report that “Peritoneal irrigation does not have any advantage over suction alone in complicated appendicitis in both adults and children. The performance of irrigation during laparoscopic appendectomy does not seem to prevent the development of IAA and wound infections
in neither adults nor paediatric patients”. WSES recommendation is “to perform suction only in complicated appendicitis patients with intra-abdominal collections undergoing laparoscopic appendectomy” [QoE: Moderate; Strength of recommendation: Strong; 1B]). The concern regarding irrigation and lavage is that these procedures might help spread the infectious material.”

Continue reading