Prophylactic nasogastric decompression after abdominal surgery

“The prophylactic use of nasogastric tubes after abdominal operations, flexible tubes inserted through the nose, pharynx, oesophagus and into the stomach, has happened only in the last century, becoming so prevalent that it has been variously described as “the standard of care” (Montgomery 1996), “traditionally used by most surgeons” (Lee 2002), “common practice” (Cunningham 1992, Sakadamis 1999, Manning 2001), “unquestioned” (Savassi-Rocha 1992), and “routine” (Wolff 1989). What is to be achieved by this prophylaxis is gastric decompression, decreased likelihood of nausea and vomiting, decreased distention, less chance of pulmonary aspiration and pneumonia, less chance of wound separation and infection, less chance of fascial dehiscence and hernia, earlier return of bowel function, and earlier hospital discharge.”

Continue reading →

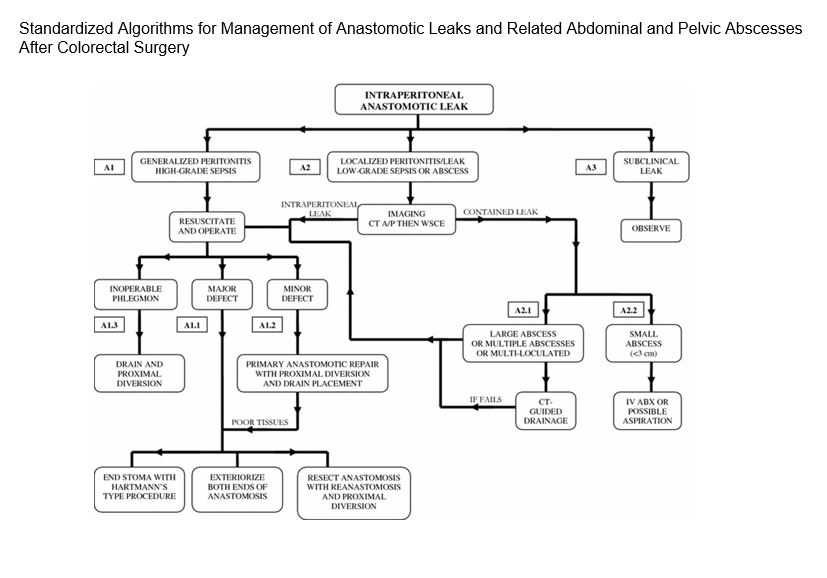
Standardized Algorithms for Management of Anastomotic Leaks and Related Abdominal and Pelvic Abscesses After Colorectal Surgery

“The risk factors and incidence of anastomotic leak following colorectal surgery are well reported in the literature. However, the management of the multiple clinical scenarios that may be encountered has not been standardized.”
In this study, “management scenarios were divided into those for intraperitoneal anastomoses, extraperitoneal (low pelvic) anastomoses, and anastomoses with proximal diverting stomas. Management options were then based on the clinical presentation and radiographic findings and organized into three interconnected algorithms.”

Recommendations for the management of intraperitoneal anastomotic leak with references to the pertinent sections of this article for more information. KEY: IV ABX=intravenous antibiotics; CT=computed tomographic; WSCE=water soluble contrast enema; CT A/P=computed tomographic scan of the abdomen and pelvis
Continue reading →

Management of Postoperative Complications Following Operations for Breast Cancer

At bottom of post Surgical Clinics of North America issue on postoperative complications.

“The reported complication rates after breast cancer surgery are low, with rates ranging
from 2% to 50%, and are reportedly more common when performed in conjunction with axillary surgery and immediate breast reconstruction. A breakdown by procedure type has shown morbidity rates between 5% and 50% after mastectomy and from 3% to 35% after lumpectomy with or without reconstruction.”

Hilli
Continue reading →

Permanent Hypoparathyroidism After Thyroidectomy

“Hypoparathyroidism (HP) is a recognized but serious complication of thyroidectomy. Conventional techniques for parathyroid autograft (PA) occur with the insertion of parathyroid slices in muscle pockets and have a published incidence of HP of 4%–8%. The purpose of this study was to analyze the incidence of HP after thyroidectomy at our center, where we have used a modified technique for PA.”

Continue reading →

Techniques for intraoperative evaluation of bowel viability inmesenteric ischemia:

“Acute mesenteric ischemia (AMI) accounts for approximately 1:1000 acute hospital admissions in the United States, and the incidence is on the rise likely due to an aging population as well as the prolonged survival of critically ill patients. AMI can be caused by a reduction in blood flow from arterial occlusion, venous occlusion, arterial vasospasm, or a low-flow state. Regardless of the etiology of the disease, rapid diagnosis and treatment of AMI is of critical importance”

Continue reading →

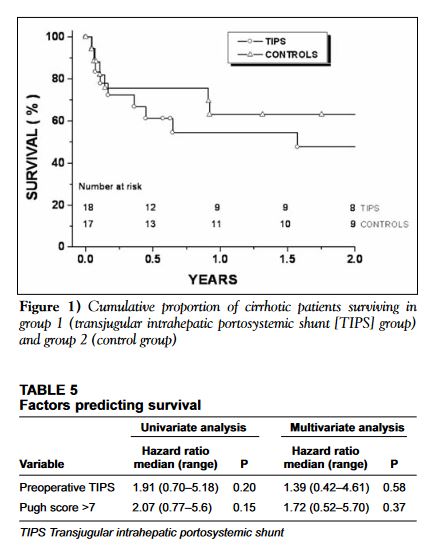
Transjugular intrahepatic portosystemic shunt before abdominal surgery in cirrhotic patients

“Abdominal surgery is occasionally needed in cirrhotic patients and is associated with high morbidity and mortality rates. It has been suggested that the main determinant of short- and long-term survival is the degree of liver failure, as evaluated by the presence of ascites, low serum albumin level and coagulation disorders. In addition, the degree of portal
hypertension may be an independent predictor for operative bleeding, postoperative ascites leakage or variceal rupture; this may also influence survival. Transjugular intrahepatic portosystemic shunt (TIPS) placement is much less invasive than surgical shunts and can be performed in patients with a significant degree of liver insufficiency. Therefore, it has been suggested that preoperative TIPS placement may improve the prognosis of cirrhotic patients, submitted to abdominal surgery.”

Continue reading →

Anorectal Infections in Neutropenic Leukemia Patients

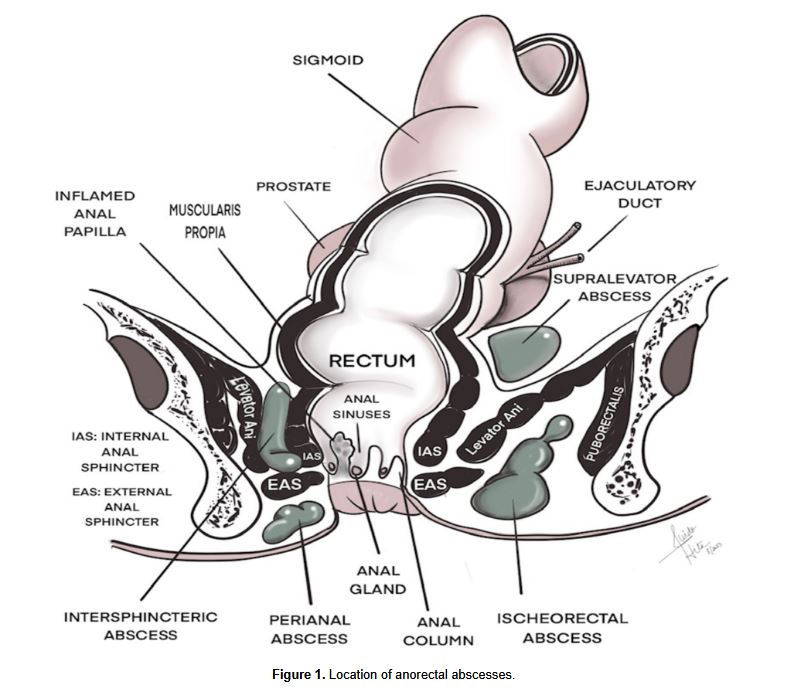
“Anorectal infections in neutropenic leukemia patients are a significant and potentially life-threatening complication. The pathogenesis of this condition is not entirely understood and believed to be multifactorial, including mucosal injury as a result of cytotoxic drugs, profound neutropenia and impaired host defense. Establishing an early diagnosis is key and often made clinically on the basis of signs and symptoms, but also from imaging studies demonstrating perianal inflammation or fluid collection. The management of anorectal infections in neutropenic leukemia patients is not straightforward, as there are no well-conducted studies on this entity.”

Continue reading →