Article of interest: Clinical practice guideline for the management of anorectal abscess, fistula-in-ano, and rectovaginal fistula

Vogel JD, et al. Clinical Practice Guideline for the Management of Anorectal Abscess, Fistula-in-Ano, and Rectovaginal Fistula. Dis Colon Rectum. 2016 Dec;59(12):1117-1133. Full-text for Emory users.

Recommendations: Treatment of Rectovaginal Fistulas (p. 1123-1125)

Continue reading

The utility of oxygen therapy for treating pneumothorax

Hallifax R, et al. (2022). Pneumothorax. In: Broaeddus CV. (Ed.) Murray & Nadel’s Textbook of Respiratory Medicine, 7th ed.

“Evidence from a small study in 1971 suggests that use of 100% oxygen in patients with spontaneous pneumothorax can increase the rate of absorption fourfold compared to air (on the basis of mean reduction in pneumothorax size of 4.8 and 18 cm 2 /day, respectively). The rationale is that by reducing the partial pressure of nitrogen in the inspired gas, and thus in pleural capillaries, the rate of nitrogen absorption from the pneumothorax is increased, thereby increasing the rate of resolution of the pneumothorax.” (p. 1545)

Continue reading

“Waking up the next morning”: surgeons’ emotional reactions to adverse events

Luu S, et al. Waking up the next morning: surgeons’ emotional reactions to adverse events. Med Educ. 2012 Dec;46(12):1179-88. Full-text for Emory users.

Results: Surgeons expressed feeling unique and alone in the depths of their reactions to adverse events and consistently described four phases of response, each containing cognitive and emotive components, following such events. The initial phase (the kick) involved feelings of failure (‘Am I good enough?’) experienced with a significant physiological response. This was shortly followed by a second phase (the fall), during which the surgeon experienced a sense of chaos and assessed the extent of his or her contribution to the event (‘Was it my fault?’). During the third phase (the recovery), the surgeon reflected on the adverse event (‘What can I learn?’) and experienced a sense of ‘moving on’. In the fourth phase (the long-term impact), the surgeon experienced the prolonged and cumulative effects of these reactions on his or her own personal and professional identities. Surgeons also described an effect on their clinical judgement, both for the case in question (minimisation) and future cases (overcompensation).

Conclusions: Surgeons progress through a series of four phases following adverse events that are potentially caused by or directly linked to surgeon error. The framework provided by this study has implications for teaching, surgeon wellness and surgeon error.

Continue reading

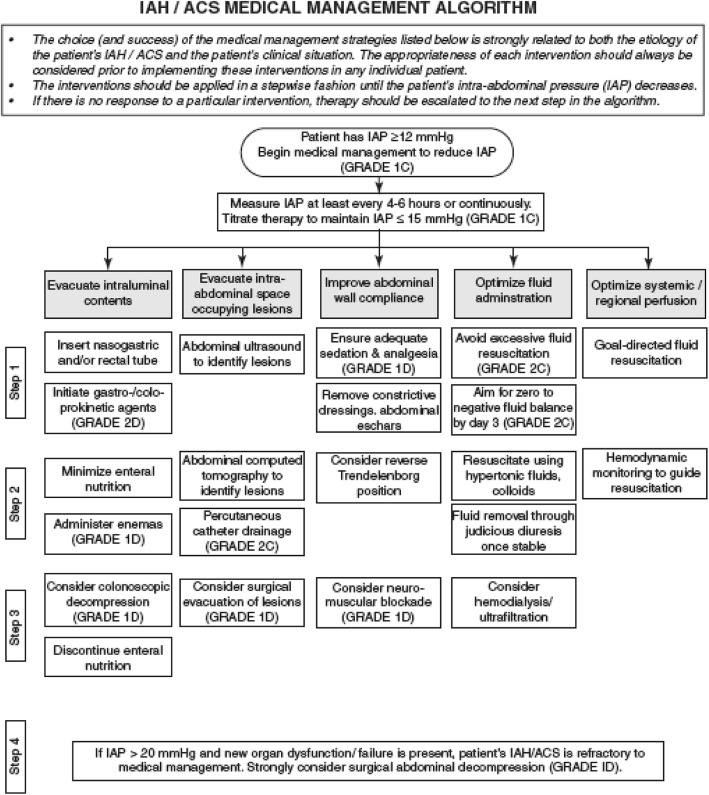
Article of interest: A Clinician’s Guide to Management of Intra-abdominal Hypertension and Abdominal Compartment Syndrome in Critically Ill Patients

De Laet IE, et al. A Clinician’s Guide to Management of Intra-abdominal Hypertension and Abdominal Compartment Syndrome in Critically Ill Patients. Crit Care. 2020 Mar 24;24(1):97.

Continue reading

Article of Interest: Combined Nivolumab and Ipilimumab or Monotherapy in Untreated Melanoma

Larkin J, Chiarion-Sileni V, Gonzalez R, et al. Combined Nivolumab and Ipilimumab or Monotherapy in Untreated Melanoma. N Engl J Med. 2015 Jul 2;373(1):23-34. Erratum in: N Engl J Med. 2018 Nov 29;379(22):2185. Free full-text.

Results: The median progression-free survival was 11.5 months (95% confidence interval [CI], 8.9 to 16.7) with nivolumab plus ipilimumab, as compared with 2.9 months (95% CI, 2.8 to 3.4) with ipilimumab (hazard ratio for death or disease progression, 0.42; 99.5% CI, 0.31 to 0.57; P<0.001), and 6.9 months (95% CI, 4.3 to 9.5) with nivolumab (hazard ratio for the comparison with ipilimumab, 0.57; 99.5% CI, 0.43 to 0.76; P<0.001). In patients with tumors positive for the PD-1 ligand (PD-L1), the median progression-free survival was 14.0 months in the nivolumab-plus-ipilimumab group and in the nivolumab group, but in patients with PD-L1-negative tumors, progression-free survival was longer with the combination therapy than with nivolumab alone (11.2 months [95% CI, 8.0 to not reached] vs. 5.3 months [95% CI, 2.8 to 7.1]). Treatment-related adverse events of grade 3 or 4 occurred in 16.3% of the patients in the nivolumab group, 55.0% of those in the nivolumab-plus-ipilimumab group, and 27.3% of those in the ipilimumab group.

Continue reading

The Confusion Assessment Method (CAM) for the ICU-7 Delirium Severity Scale

Khan BA, et al. The Confusion Assessment Method for the ICU-7 Delirium Severity
Scale: A Novel Delirium Severity Instrument for Use in the ICU
. Crit Care Med. 2017 May;45(5):851-857.

Measurements and Main Results: Patients received the CAM-ICU, Richmond Agitation-Sedation Scale (RASS), and Delirium Rating Scale-Revised (DRS-R)-98 assessments. A 7-point scale (0-7) was derived from responses to the CAM-ICU and RASS items. CAM-ICU-7 showed high internal consistency (Cronbach’s alpha=0.85) and good correlation with DRS-R-98 scores (correlation coefficient=0.64). Known-groups validity was supported by the separation of mechanically ventilated and non-ventilated assessments. Median CAM-ICU-7 scores demonstrated good predictive validity with higher odds (OR=1.47; 95% CI=1.30-1.66) of inhospital mortality, and lower odds (OR=0.8; 95% CI=0.72-0.9) of being discharged home after adjusting for age, race, gender, severity of illness, and chronic comorbidities. Higher CAM-ICU-7 scores were also associated with increased length of ICU stay (p=0.001).

Continue reading