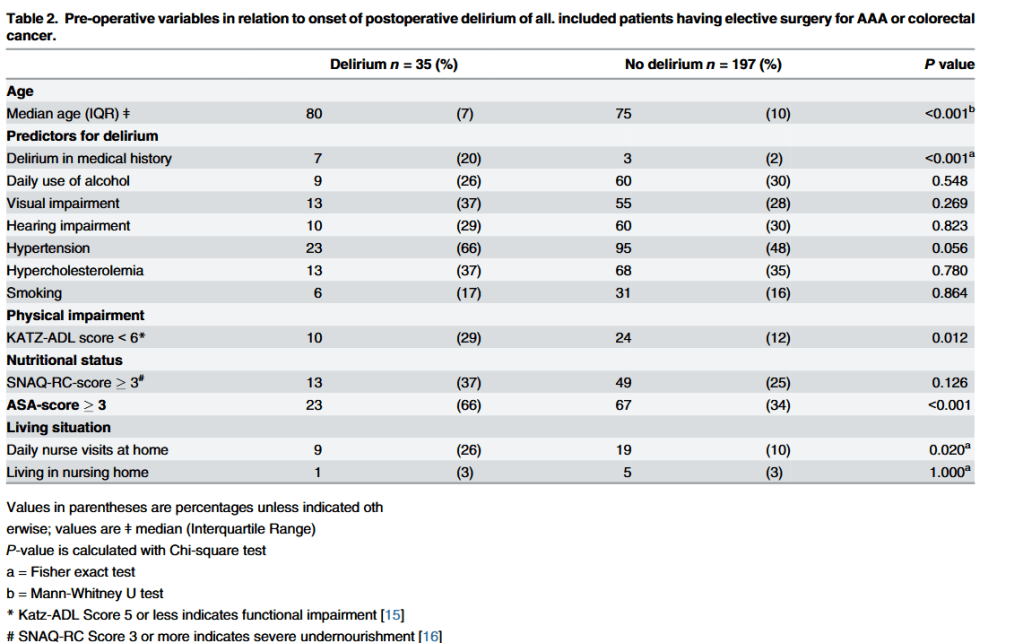
Risk Factors and Outcomes for Postoperative Delirium after Major Surgery in Elderly Patients

“The number of people over 65 years is increasing and will continue to do so over the coming decades. Similarly, the number of elderly patients requiring surgery is expected to increase.
Delirium is a common and serious problem in hospitalized patients, especially in the elderly.
Postoperative delirium is associated with an increase in postoperative complications, a decrease in functional capacity, a prolonged hospital stay and a direct increase of healthcare costs.
Early identification of patients at risk for delirium is important because adequate well timed
interventions could prevent occurrence of delirium and the related detrimental outcome.
Several prediction models have been developed, including multiple risk factors for postoperative delirium. However, these studies are of varying quality and each with a heterogeneous population.
Measuring frailty may be a more sensitive marker of determining post-operative delirium. However, to this date, there is no consensus on a clear definition and quantification of
frailty. Several assessment instruments have been developed for frailty during the last decades.
The most evidence based process to identify frail patients at this moment is comprehensive
geriatric assessment. However, this is a resource intensive, time consuming process and therefore not suitable for clinical practice”
Continue reading →

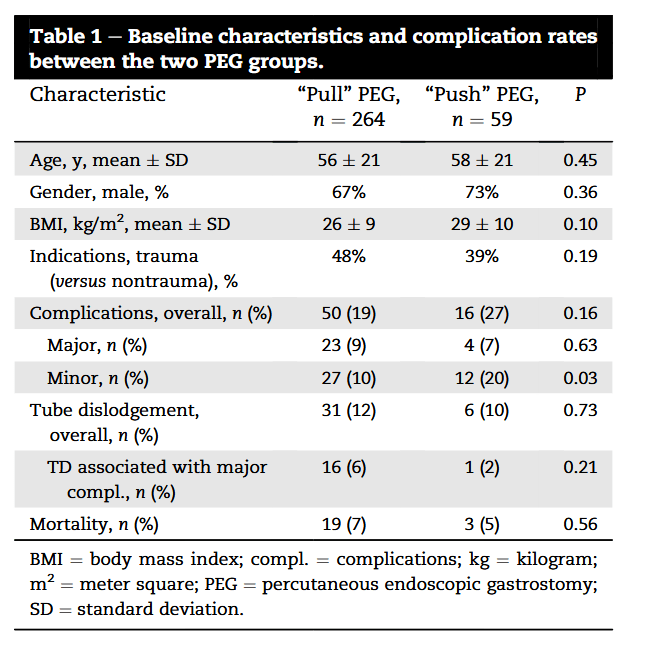
Comparing Outcomes Between “Pull” Versus “Push” Percutaneous Endoscopic Gastrostomy in Acute Care Surgery: Under-Reported Pull Percutaneous Endoscopic Gastrostomy Incidence of Tube Dislodgement

“Percutaneous endoscopic gastrostomy (PEG) tube placement is a commonly performed procedure in trauma patients.Since the establishment of the acute care surgery (ACS)
model, the role of ACS in PEG tube placement in many institutions has expanded. The incidence of PEG tube complications has been under-reported in the literature and varies
widely among the patient populations studied and the definition of complications utilized. Major and minor complications may range from 3% to 26%. Our institution, under an ACS model, has previously reported an overall 25% complication rate with 10% major and 14% minor complications associated with pull PEG.”

Continue reading →

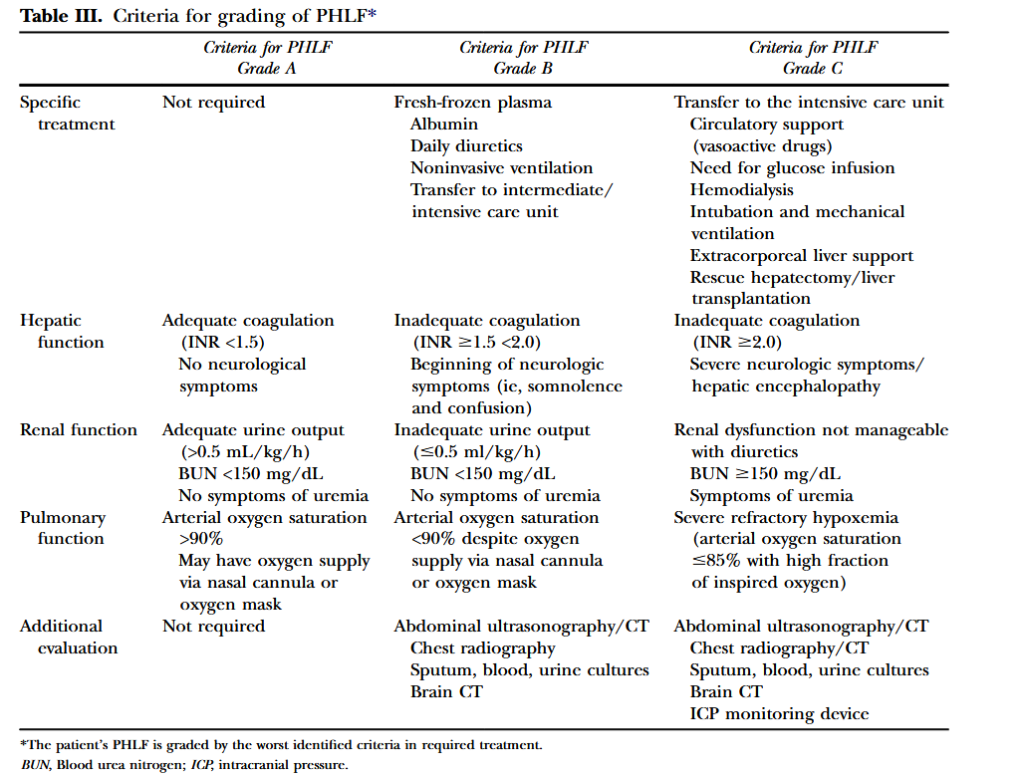
Posthepatectomy liver failure: A definition and grading by the International Study Group of Liver Surgery (ISGLS)

“Liver resection is used increasingly for the management of a variety of benign and malignant conditions. These data have paralleled substantial advances in perioperative management and operative techniques that have improved the safety of, and extended the indications for, liver resection over the past 2 decades. Extended liver resections, liver resections in diseased liver or liver parenchyma affected by chemotherapy, and repeat
or staged liver resections are being used to achieve curative resection and extend long-term survival. The resulting small functional remnant liver volumes and compromised liver function in these patients increase the risk for the development of posthepatectomy liver failure (PHLF). Despite the introduction of functional and imaging measures to assess preoperatively the size and function of the future liver remnant, as well as the use of
portal vein embolization as a preventive intervention, PHLF remains a major concern and has been shown to be a predominant cause of hepatectomy-related mortality.”

Continue reading →

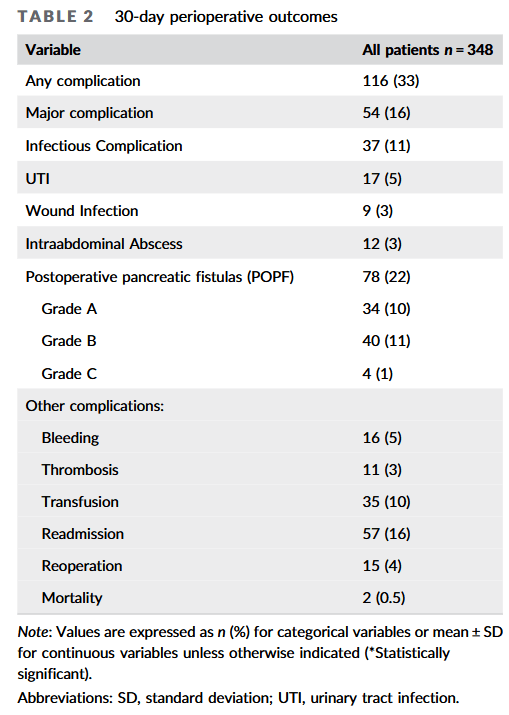
Implications of leukocytosis following distal pancreatectomy splenectomy (DPS) and association with postoperative complications

“Distal pancreatectomy with splenectomy (DPS) is performed to remove pathology of the body and/or tail of the pancreas. The spleen and the left side of the pancreas share blood supply, and often tumor involvement, thus splenectomy is often performed along with distal
pancreatectomy. DPS is an operation that carries a greater than 30% risk of postoperative complications, including infection, postoperative pancreatic fistula (POPF), intraabdominal abscesses, and pneumonia, among others. In addition to these immediate postoperative
complications, splenectomy itself is known to confer long‐term susceptibility to infection, sepsis, thrombosis, and other sequelae. Our goal was to identify factors that could prompt early investigation and treatment of both infectious and major complications.”

Continue reading →

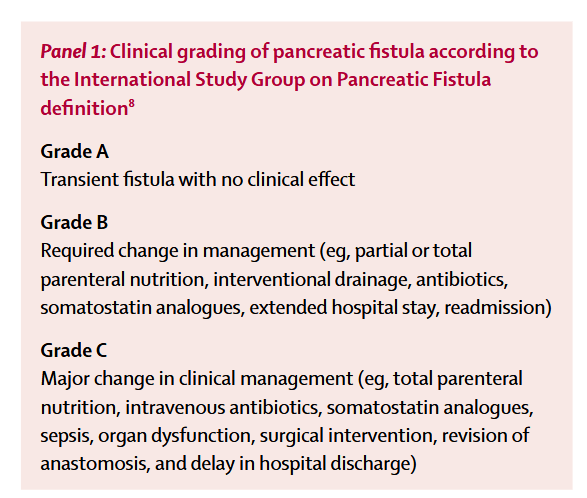
Efficacy of stapler versus hand-sewn closure after distal pancreatectomy (DISPACT)

“Resections of the pancreas reaching to the left of the superior mesenteric vein are defined as distal pancreatectomy. Most distal pancreatectomies are done electively (84%) as a result of chronic pancreatitis (24%), other benign diseases (22%), malignant diseases (18%), neuroendocrine tumours (14%), and pancreatic pseudocysts (6%). The remaining 16% are emergency cases after abdominal trauma or miscellaneous pathological
diagnoses. A systematic review supports the evidence that postoperative pancreatic fistula formation represents a major source of postoperative morbidity (13–64%) and is associated with several further complications, such as intra-abdominal abscess, wound infection, sepsis, malabsorption, and haemorrhage.
A meta-analysis of the most favoured and reported techniques (stapler trans-section and closure vs scalpel trans-section and hand-sewn closure of the pancreatic remnant) did
not define the optimum surgical technique of pancreatic stump closure. Therefore, the multicentre randomised DISPACT trial was designed to assess the effect of stapler
versus hand-sewn closure on formation of postoperative pancreatic fistula after distal pancreatectomy.”

Continue reading →

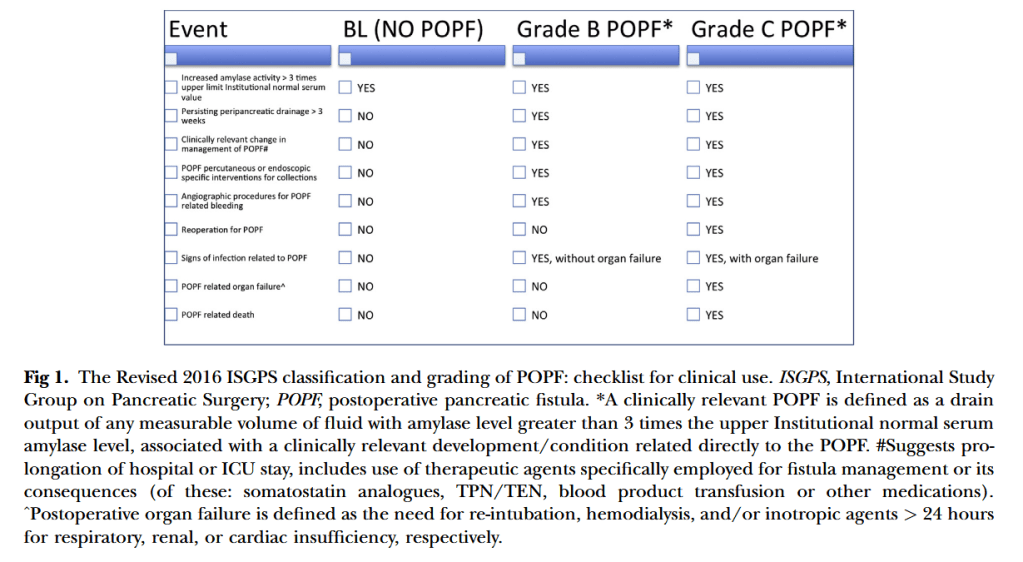
2016 update of the International Study Group (ISGPS) definition and grading of postoperative pancreatic fistula

“Eleven years after its definition, postoperative pancreatic fistula (POPF) still remains one of the most harmful complications after pancreatic resection. Despite all the advances and technical modifications developed during this past decade to prevent POPF, the incidence of this dreaded complication still ranges between 3–45 % of pancreatic operations at high-
volume centers. Updating the ISGPF classification is both relevant and clinically important,
because POPF remains the single main determinant of serious postoperative morbidity and mortality related to pancreatic resection and plays a major role in terms of operation-related mortality, morbidity, hospital stay, and economic impact.”

Continue reading →

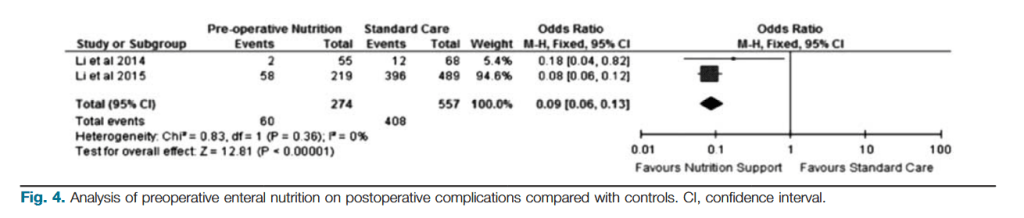
Does preoperative enteral or parenteral nutrition reduce postoperative complications in Crohn’s disease patients?

“Surgery is frequently needed in Crohn’s Disease (CD) patients who have malnutrition. Patients with CD are at a risk of malnutrition secondary to decreased oral intake, malabsorption, and inflammation. The prevalence of malnutrition in IBD patients is profound: 60–80% of IBD patients are anemic, 39–81% are iron deficient, 20–60% are vitamin B12
deficient, 36–54% are folate deficient, and 25–80% have hypoalbuminemia. This high prevalence of malnutrition presents a challenge in the surgical management of CD patients because poor preoperative nutritional status has been linked to increase postoperative complications.
Therefore, nutritional optimization using enteral nutrition (EN) and total parenteral nutrition (TPN) have been used for many years to improve the nutritional status of CD patients in hopes of decreasing postoperative complications.”

Continue reading →