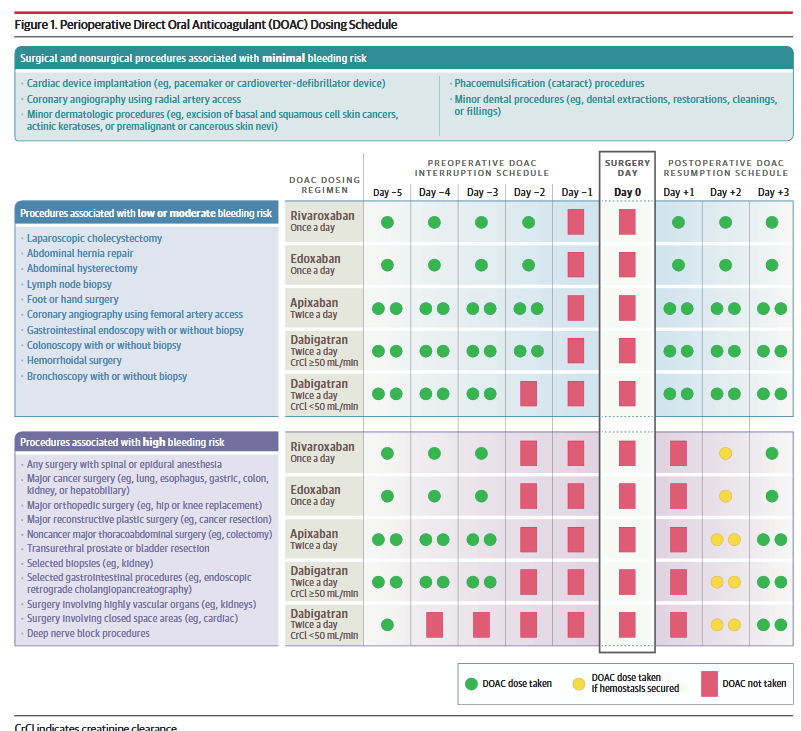
Perioperative Management of Patients Taking Direct Oral Anticoagulants

“Direct oral anticoagulants (DOACs), including apixaban, rivaroxaban, edoxaban, and dabigatran, are widely used anticoagulants. Approximately 4 million patients in the
US are currently being treated with DOAC therapy. DOACs are indicated for stroke prevention in patients with atrial fibrillation and for the prevention and treatment of venous thromboembolism. For these conditions, DOACs have advantages compared with war-
farin that include a lower risk of bleeding, fixed dosing that does not require coagulation test monitoring, and fewer potential drug-drug interactions.
Knowing how to advise patients who are taking a DOAC and need a surgical procedure (a surgical operation typically with general/spinal anesthetic) or nonsurgical procedure (a nonsurgical intervention, such as a biopsy or colonoscopy, that typically does not require general/spinal anesthetic) is important because approximately 20% of DOAC-treated patients undergo an elective or urgent procedure annually. Moreover, DOAC use is
increasing, especially among older patients for whom a surgical or nonsurgical procedure is most commonly performed.Perioperative DOAC management requires careful decisions about preoperative interruption and postoperative DOAC resumption to minimize the risks of thromboembolism and bleeding. Surgical-site bleeding increases the likelihood of reoperation and delays resumption of anticoagulant therapy, which increases the risk for
thromboembolism,”
Continue reading →

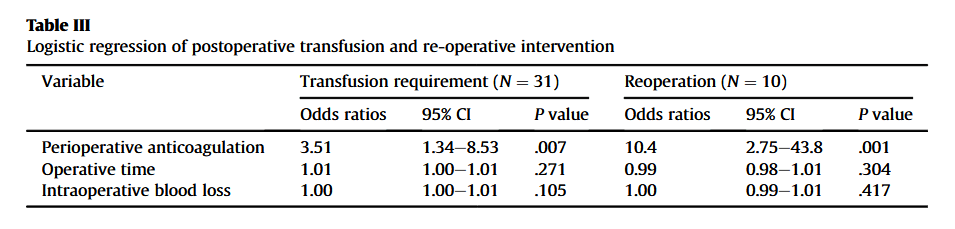
Postoperative bleeding after complex abdominal wall reconstruction

“Rates of postoperative bleeding and transfusion are either widely variable or often unreported. As a high-volume center, we have anecdotally appreciated significant rates of each but admittedly have not accurately reported the degree of this specific morbidity in
our practice. This study aims to quantify postoperative blood loss, rates of blood transfusion, and the incidence of operative or endovascular intervention for bleeding, as well as associated risk factors contributing to this morbidity in patients undergoing open TAR.”

Continue reading →

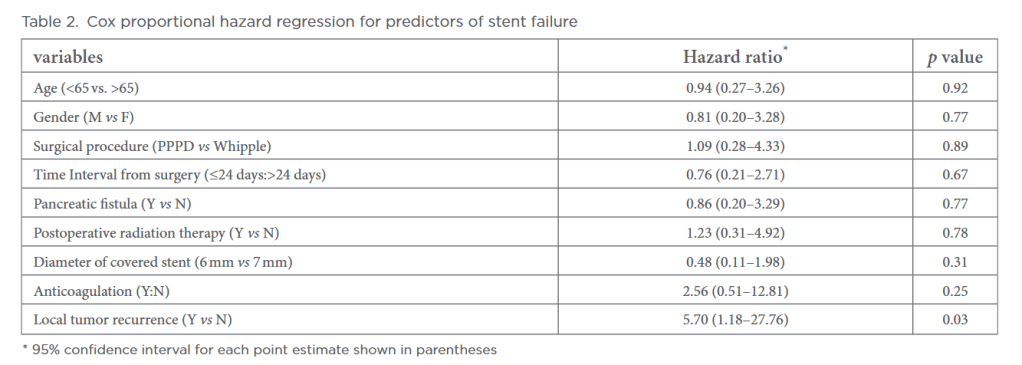
Covered stent placement for gastroduodenal artery stump hemorrhage after pancreaticoduodenectomy

“Post- pancreaticoduodenectomy (PD) hemorrhage is a rare but fatal complication that accounts for 10–40% of post-operative mortality.1,2 In such patients, successful surgical
treatment is compromised due to extensive inflammatory changes caused by recent dissections. Therefore, endovascular treatment is considered as the first line treatment
especially in cases of delayed hemorrhage (occurring 24 h after surgery) from the hepatic artery (HA). Transcatheter embolization and covered stent placement are the most
common endovascular techniques. However, transcatheter embolization typically involves sacrificing the major HA, which frequently causes severe hepatic ischemia or infarction.”

Continue reading →

Post-pancreatectomy haemorrhage management stratified according to ISGPS grading

“Despite improvements in the perioperative care of patients undergoing pancreatic surgery, the risk of major complications including anastomotic leak (6–24%), post-operative pancreatic fistula (POPF) (10–40%) and delayed gastric emptying (20–34%) persist. Post-pancreatectomy haemorrhage (PPH) is a less common, but particularly hazardous complication with mortality rates of up to 40%. However, varying definitions and incidences of PPH have been previously reported, which have hindered comparison of optimal treatment modalities.”

Continue reading →

Relationship Between the Number of Intersections of Staple Lines and Anastomotic Leakage

“The number of intersections of staple lines is associated with anastomotic leakage, and the inversion technique is a useful method for avoiding anastomotic leakage. Using an appropriate technique by skilled operator, double stapling technique for laparoscopic
anterior resection is safe and feasible.”

“

Laparoscopic intracorporeal colorectal anastomosis with double stapling technique is difficult because of the unsuitable cutting angle associated with using a linear stapler in the narrow pelvic cavity. Consequently, we sometimes have used multiple stapler firings during division of the rectum. Because of the long and tilted linear staple line placed on the rectal stump, a circular anastomotic plane can create multiple intersections of staple lines and dog-ears. Anastomotic leakage is a major problem in patients with colorectal cancer who have
undergo laparoscopic surgery. Despite technical improvements in laparoscopic surgery, recent studies have reported that the anastomotic leakage rate remains at 6.3% to 13.7%.” (Lee)

Lee
Continue reading →

Postpancreatectomy hemorrhages: risk factors and outcomes

One discussion this week involved etiologies of postpancreatectomy hemorrhage.


Reference: Yekebas EF, et al. Postpancreatectomy hemorrhage: diagnosis and treatment: an analysis in 1669 consecutive pancreatic resections. Annals of Surgery. 2007 Aug;246(2):269-280. doi:10.1097/01.sla.0000262953.77735.db

Summary: With the purpose of creating algorithms for managing postpancreatectomy hemorrhage (PPH), Yekebas et al (2007) restrospectively analyzed more than 1669 pancreatic resections conducted between 1992 and 2006.  They concluded that the prognosis of postpancreatectomy hemorrhage (PPH) is primarily dependent on the presence of “preceding pancreatic fistula” (p.269).

Continue reading →

Article of interest: Bleeding complications after pancreatic surgery: interventional radiology management

Biondetti P, Fumarola EM, Ierardi AM, Carrafiello G. Bleeding complications after pancreatic surgery: interventional radiology management. Gland Surg. 2019 Apr;8(2):150-163. doi: 10.21037/gs.2019.01.06.

Surgical intervention in the pancreas region is complex and carries the risk of complications, also of vascular nature. Bleeding after pancreatic surgery is rare but characterized by high mortality. This review reports epidemiology, classification, diagnosis and treatment strategies of hemorrhage occurring after pancreatic surgery, focusing on the techniques, roles and outcomes of interventional radiology (IR) in this setting. We then describe the roles and techniques of IR in the treatment of other less common types of vascular complications after pancreatic surgery, such as portal vein (PV) stenosis, portal hypertension and bleeding of varices.