Management of Esophageal Perforation

Lindenmann J, Matzi V, Neuboeck N, et al. Management of esophageal perforation in 120 consecutive patients: clinical impact of a structured treatment algorithm. J Gastrointest Surg. 2013 Jun;17(6):1036-43.

Full-text for Emory users.
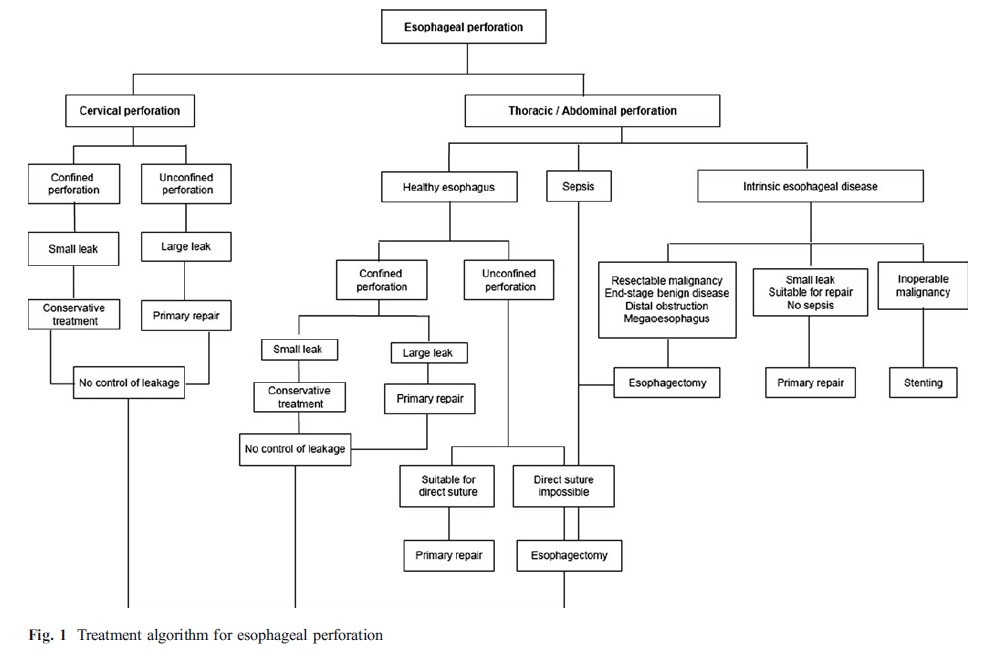
Click to enlarge.

Results: Iatrogenic perforation was the most frequent cause of esophageal perforation (58.3 %); Boerhaave’s syndrome was detected in 15 cases (6.8 %). Surgery was performed in 66 patients (55 %), 17 (14 %) patients received conservative treatment and 37 (31 %) patients underwent endoscopic stenting after tumorous perforation. Statistically significant impact on mean survival had Boerhaave’s syndrome (p = 0.005), initial sepsis (p = 0.002), pleural effusion/empyema (p = 0.001), mediastinitis (p = 0.003), peritonitis (p = 0.001), and redo-surgery (p = 0.000). Overall mortality rate was 11.7 %, in the esophagectomy group 17 % and in the patients with Boerhaave’s syndrome 33.3 %.
Continue reading →

Iatrogenic bladder injury and prevention of catheter-related bacteriuria

Literature review conducted and presented by Dr. Clara Farley

EUA guidelines on iatrogenic bladder trauma:

  • Repair in two layers with absorbable sutures
  • Postop bladder drainage is required for 7-14 days
  • Cystoscopy is advised

Bacteriuria in patients with indwelling catheters occurs at a rate of approx. 3-10% per day of catheterization:

  • Of those with bacteriuria, approx. 10-25% develop UTI (GU or systemic symptoms)
  • 4% of less develop catheter related bacteremia

Association between the rate of UTI and duration of catheterization:

  • 15% at 3 days
  • 68% at 8 days

Continue reading →

Afferent loop syndrome

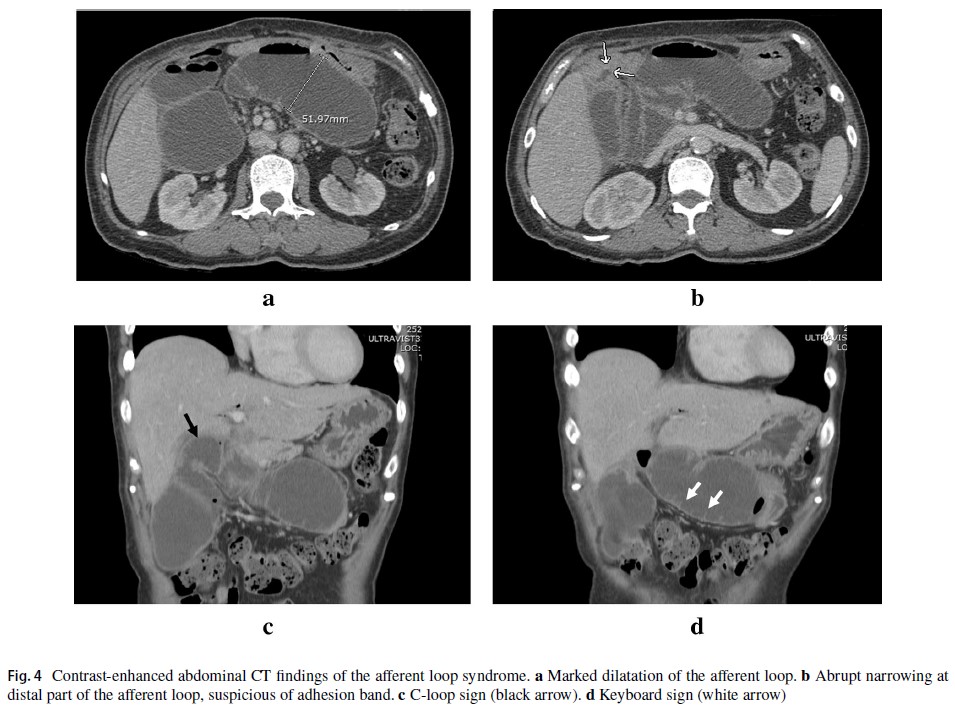
Termsinsuk P, Chantarojanasiri T, Pausawasdi N. Diagnosis and treatment of the afferent loop syndrome. Clin J Gastroenterol. 2020 Oct;13(5):660-668.

“ALS is a rare condition with the incidence ranging from 0.2 to 1.0% depending on the type of operation and anastomotic limb reconstruction. ALS has been reported in 0.3–1.0% of patients after total gastrectomy with Billroth II or Roux-en-Y reconstruction, 1% after laparoscopic distal gastrectomy with Billroth II reconstruction, and 0.2% after distal gastrectomy with Roux-en-Y reconstruction [4–6]. Other operations of which ALS can occur include total gastrectomy with loop esophagojejunostomy with simple or pouch Roux-en-Y reconstruction and pancreaticoduodenectomy with conventional loop and Roux-en-Y reconstruction; nonetheless, the data on incidence were limited [7].”

Continue reading →

ASCRS Clinical Practice Guidelines for the Treatment of Left-Sided Colonic Diverticulitis

Hall J, Hardiman K, Lee S, et al. The American Society of Colon and Rectal Surgeons Clinical Practice Guidelines for the Treatment of Left-Sided Colonic Diverticulitis. Dis Colon Rectum. 2020 Jun;63(6):728-747.

Full-text for Emory users.

“This publication summarizes the changing treatment paradigm for patients with left-sided diverticulitis. Although diverticular disease can affect any segment of the large intestine, we will focus on left-sided disease. Bowel preparation, enhanced recovery pathways, and prevention of thromboembolic disease, while relevant to the management of patients with diverticulitis, are beyond the scope of these guidelines and are addressed in other ASCRS clinical practice guidelines.”

Continue reading →

Trocar injuries in laparoscopy

Nishimura M, et al. Complications Related to the Initial Trocar Insertion of 3 Different Techniques: A Systematic Review and Meta-analysis. J Minim Invasive Gynecol. 2019 Jan;26(1):63-70.

Emory users, request article via ILLiad.

This systematic review aimed to investigate complications related to initial trocar insertion among 3 different laparoscopic techniques: Veress needle (VN) entry, direct trocar entry (DTE), and open entry (OE). A literature search was completed, and complications were assessed. Major vessel injury, gastrointestinal injury, and solid organ injury were defined as major complications. Minor complications were defined as subcutaneous emphysema, extraperitoneal insufflation, omental emphysema, trocar site bleeding, and trocar site infection. Arm-based network meta-analyses were performed to identify the differences in complications among the 3 techniques. Seventeen studies were included in the quantitative analysis. DTE resulted in fewer major complications when compared with VN entry although the difference was not significant (p = .23) as well as significantly fewer minor complications (p < .001). There were no significant differences in minor complications when comparing OE and DTE (p = .74). Fewer major complications were observed with OE compared with VN entry although the difference was not significant (p = .31). There were significantly fewer minor complications for patients who underwent OE (p = .01). DTE patients experienced the least number of minor complications followed by VN entry and OE. In conclusion, major complications are extremely rare, and all 3 insertion methods can be performed without mortality.

Continue reading →

Surgical management of mycotic aortic aneurysms

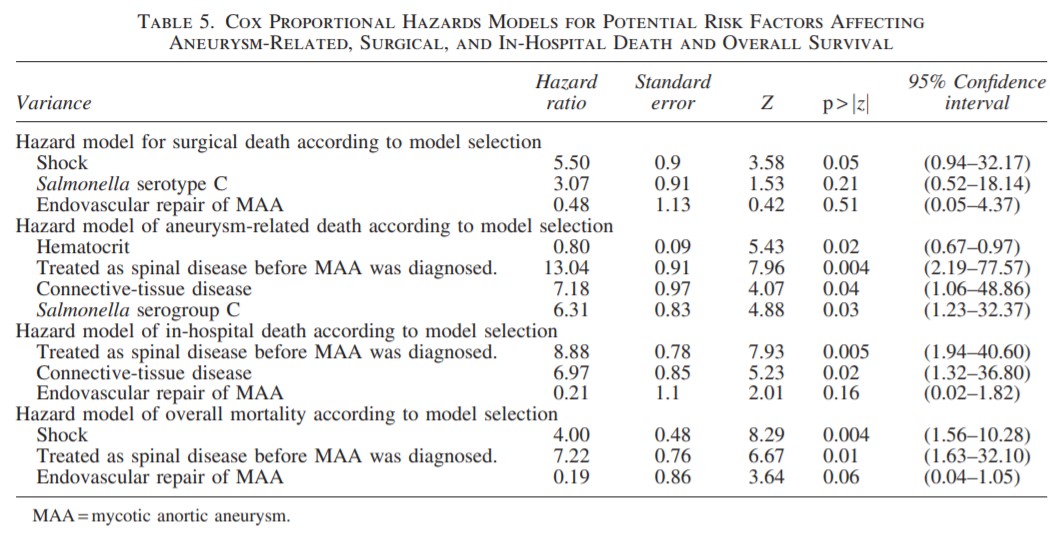
Huang YK, et al. Clinical, microbiologic, and outcome analysis of mycotic aortic aneurysm: the role of endovascular repair. Surg Infect (Larchmt). 2014 Jun;15(3): 290-8.

Free full-text.

Click to enlarge.

Results: All of the patients had positive blood cultures, radiologic findings typical of MAA, and clinical signs of infection (leukocytosis, fever, and elevated C-reactive protein). The mean age of the patients was 63.8±10.6 y and the mean period of their follow up was 35.7±39.3 mo. Twenty-nine patients with MAAs underwent traditional open surgery, 11 others received endovascular stent grafts, and four MAAs were managed conservatively. The most frequent causative pathogens were Salmonella (36/44 patients [81.8%]), in whom organisms of Salmonella serogroup C (consisting mainly of S. choleraesuis) were identified in 14 patients, organisms of Salmonella serogroup D were identified in 13 patients, and species without serogroup information were identified in nine patients. The overall mortality in the study population was 43.2% (with an aneurysm-related mortality of 18.2%, surgically related mortality of 13.6%, and in-hospital mortality of 22.7%).

Continue reading →